
Protrusive Dental Podcast
Jaz Gulati
0
The Protrusive Dental Podcast is a forward-thinking dental podcast hosted by Jaz Gulati. It covers a wide range of topics in dentistry, aiming to provide education and insights for dental professionals. The podcast features interviews with experts and discussions on clinical techniques, practice management, and the latest advancements in dental care.
Episodi
-
 Thoughts Become Things - How to Be Happier in Dentistry - IC079 02.10.2026 48minWhen a filling doesn’t go to plan, how many times do you replay it on the drive home?Have you fallen out of love with dentistry — or just with the way you’re experiencing it right now?Why do the habits that could help your headspace get forgotten by Wednesday?And when did you last ask yourself: have my thoughts been serving me today?This is an Interference Cast episode — no margins, no bonding protocols. Jaz is joined by Neo Positivity, a former Camden, New Jersey police officer turned mindset speaker, who now spends his time in dental practices in the US and the UK with one message: thoughts become things.Neo is big energy, and not every part of his philosophy will land for everyone — it doesn’t need to. Underneath it are habits any dentist can use tomorrow: stepping back from the “what if” spiral after a treatment goes wrong, catching autopilot thinking, remembering how badly you once wanted this job, and building reminders into the day so you actually follow through. Jaz leaves with a very personal takeaway about the version of himself that shows up at home.This episode discusses suicide in the dental profession. If you’re struggling, please talk to someone today — in the UK and Ireland, Samaritans are free and available 24/7 on 116 123; in the US, call or text 988. The Canmore Trust (thecanmoretrust.co.uk) supports dental professionals affected by suicide.What You’ll Take From This EpisodeStep back from the thought — the press-conference technique for the “what if I get sued?” spiral.Watch what you water — why the thoughts you rehearse most become the easiest to repeat.Get home first — the step to take before you quit a job, or dentistry.Reach for the cookie jar — using past wins to reset a bad day and repair a strained nurse relationship.Lead the ripple — why a leader who walks out of the wellbeing session undoes it.Highlights of This Episode00:00 TEASER00:57 Why Mental Wellbeing Belongs on a Dental Podcast03:49 From Police Officer to Mindset Coach09:12 Burnout in Dentistry: Facing the Problem Honestly10:24 How to Stop Ruminating After a Treatment Goes Wrong14:07 Your Thoughts Aren't Facts: The Press Conference Technique16:10 Watering Seeds: How Repeated Thoughts Rewire Your Brain20:03 Autopilot Thinking in the Dental Practice22:31 Midroll25:52 Energy, Vibe and the Patients You Attract30:30 How to Fix a Difficult Relationship With Your Dental Nurse33:14 The Cookie Jar: Using Past Wins to Reset Your Mood33:54 Burnout or the Wrong Practice? Before You Quit Dentistry39:57 Remember How Badly You Wanted to Be a Dentist41:18 Leading by Example: Building a Positive Practice Culture44:53 Accountability Partners and the Daily Mindset Check-In46:51 Takeaways, Resources and Wrap-Up50:31 OUTROFrom the GuestNeo Positivity speaks to dental practices, conferences and teams, visiting practices and speaking at lunch breaks with his “Thoughts Become Things” message. His book, Your ATM (“Your Ability to Manifest”), is out in print and as an audiobook, and he produces short morning-huddle videos for practice teams.👉 neopositivity.com — book Neo for your practice, and find Your ATMReferences & Further ReadingBooks mentioned in this episode:Eckhart Tolle — The Power of Now. On living in the present moment.Michael A. Singer — The Untethered Soul. On observing your thoughts rather than being carried by them.David Goggins — Can’t Hurt Me. Source of the “cookie jar” idea discussed in the episode.Rhonda Byrne — The Secret; and Napoleon Hill — Think and Grow Rich. The works that introduced Neo to the “thoughts become things” idea.Want more?If you enjoyed this episode, check out: Before the Breaking Point – IC071Tags#InterferenceCast #BeyondDentistry #CareerDevelopmentListen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 0.75 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcome B.AGD Subject Code: 770 Self-Improvement.Aim & Learning OutcomesAim: To help dental professionals recognise and interrupt negative thought patterns, and to give them simple, repeatable habits that support wellbeing for themselves and their teams.Learning Outcomes — by the end of this episode, dental professionals will be able to:Describe how rumination after a clinical or workplace setback reinforces itself, and apply a step-back technique to interrupt a negative thought loop.Identify practical cues and peer accountability structures that help dental professionals sustain wellbeing habits during the working day.Differentiate dissatisfaction with a working environment from dissatisfaction with dentistry itself, and outline steps to take before a major career change.
-
 How to Explain Treatment Risks and Fees Without Scaring Patients - PDP286 30.09.2026 1h 21minHow do you explain everything that could go wrong with a root canal — without the patient walking out?Why does a signed consent form protect you far less than you think?What should you say in the exact moment after you tell a patient the fee?And which single word is quietly sabotaging every future conversation you have about maintenance?This is Part 2 of our communication masterclass with Dr Zak Kara, principal dentist at Smile Stories in Bournemouth, who coaches and mentors dentists on exactly these conversations. We tackle two questions sent in by the community: how to explain risks without discouraging patients from treatment, and how to present fees — including future maintenance and complications — clearly and confidently. Expect two live role-plays (a molar root canal and a lower wisdom tooth), a respectful disagreement about whether to call people patients or clients, and the fee-presentation sequence I wish I’d had years ago, when I hated every part of talking about money.Protrusive Dental Pearl: Could They Retell It at Home?Measure a consultation by one question: was I understood? Not conversion, not uptake — understanding. The ethical approach tends to deliver the conversion anyway.The practical test: when the patient gets home and someone asks “How was the dentist today?”, can they summarise in a few sentences exactly what the appointment was about and what they need to do next? If not, the explanation isn’t finished — however thorough it felt from your side of the chair. That clarity is a skill, and it gets built deliberately.What You’ll Take From This EpisodeSix moves for explaining risk — how to make every risk proportionate, personal and paired with your plan to reduce it.A root canal consent, live — plain-English wording, an honest success rate, and the analogy that makes recovery make sense.Common vs rare risks — when a risk deserves a sentence and when it deserves a diagram.The fee presentation sequence — seven steps from the reason to the objection, and why the pause matters most.Words to ban — why fees beat prices and costs, and what to say instead of “permanent.”Maintenance without the awkwardness — setting shared responsibility up front so “redo it for free” never comes up.Highlights of This Episode00:00 TEASER00:48 How to Explain Risks and Fees to Dental Patients04:10 The Biggest Lever in Dental Communication06:53 How to Attract the Right Patients to Your Chair14:29 What Makes a Super Associate?19:58 How to Explain Treatment Risks Without Scaring Patients26:22 Root Canal Consent: A Live Role-Play33:59 Using Analogies to Explain Occlusion and TMD Risk36:08 Wisdom Tooth Consent: Common vs Rare Risks41:07 Why Consent Is a Process, Not a Signature45:45 Midroll51:34 Patients or Clients? What to Call the People You Treat55:12 How to Present Dental Fees With Confidence59:08 A Simple Framework for Presenting Fees1:12:05 When to Discuss Treatment Alternatives1:14:45 Why You Should Never Say "Permanent Crown"1:20:15 A Communication Course for Dentists1:20:51 OUTROFrom the GuestDr Zak Kara is principal dentist at Smile Stories in Bournemouth, and coaches and mentors dentists and their teams in communication. His communication course, developed with Protrusive, teaches from real consultation videos — filmed with patients’ permission — broken down play by play: what he said, why, and why he paused where he did.Pre-order the communication course here:👉 protrusive.co.uk/conversationsOnce the course is out, you’ll also get access to a 90-day accountability group with Zak and me, and the full course in podcast format for your commute.Want more?If you enjoyed this episode, check out: Presenting Treatment Plans the Comprehensive Way – PDP048Tags#PDPMainEpisodes #CommunicationListen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 1.25 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcome A.AGD Subject Code: 550 Practice Management and Human Relations.Aim & Learning OutcomesAim: To improve how dental practitioners communicate treatment risks, fees and long-term maintenance, so that patients make informed, genuinely consensual decisions without being frightened or overwhelmed.Learning Outcomes — by the end of this episode, dentists will be able to:Explain treatment risks in proportion to the individual patient’s clinical situation, using plain language, relatable analogy and a stated plan to mitigate each risk.Apply a structured sequence for presenting treatment fees that links the recommendation to the patient’s own goals and responds to objections without coercion.Describe how consent is developed across multiple touchpoints, including discussion of alternatives, shared maintenance responsibilities and checks of patient understanding.
-
 How to Talk to Patients Who Only Want One Tooth Fixed - PDP285 23.09.2026 1h 21minNEW: 15% OFF FIGS Worldwide 🌍 - use code FIGSPD15 at wearfigs.comWhat do you say when a patient comes in wanting one tooth fixed, but you can see eight more heading the same way?How do you tell a patient who has had a scale and polish every six months for twenty years that they now need something deeper without making it sound like you’re suddenly trying to sell them more dentistry?Is there a magic sentence that makes patients say yes to comprehensive care?And why can the patient you’ve known and liked for six years sometimes be harder to move forward with than a complete stranger?This is Part 1 of a two-part communication series with Dr Zak Kara — co-founder of Smile Stories in Bournemouth, and the most-returning guest on this podcast. It’s also our first-ever call-in episode: the questions came in from the community as voice notes, and this episode answers two of them. Part 2 takes on the awkward stuff — discussing fees, and communicating risk without frightening people off.Protrusive Dental Pearl: Reactive or Proactive Associate?When the diary goes quiet, what do you actually do? Wait for the practice to work some magic and fill it — or go and fill it yourself? The mentality of “the clinic supplies the patients, I just treat them” is worth a hard look. The strongest associates pull their weight: writing, school visits, social media, and simply having conversations out in public that bring people through the door.The logic behind it runs straight into the rest of this episode. You never get to do the clinical dentistry unless your communication is good — and you never get to communicate at all unless there’s someone in the chair.What You’ll Take From This EpisodeThe two ladders of readiness — clinical readiness and interpersonal readiness rise separately, and a plan gets declined when they’re badly out of step.Why “I’ll think about it” usually isn’t distrust — and the co-diagnosis move that stops you hearing it so often.The conversation circle — open on goals rather than symptoms, and close the visit by tying the recommendation back to the patient’s own words.Words that change the meeting — inflammation score instead of bleeding score, and why one word can decide whether a patient feels blamed or informed.How to present a five-figure plan — when to name the number, and what to do in the silence afterwards.Chairside scripts you can use tomorrow — permission questions, spot-the-difference, and the line that flips a treatment plan into something the patient avoids rather than buys.Highlights of This Episode00:00 TEASER00:51 How to Talk to Patients Who Only Want One Tooth Fixed03:45 Protrusive Dental Pearl: Reactive or Proactive Associate?09:27 The First Protrusive Call-In: Your Communication Questions13:40 Why There Is No Magic Sentence for Case Acceptance15:58 Co-Diagnosis: How to Make It the Patient's Own Idea22:36 The Conversation Circle: Start With Goals, End With Goals26:58 Why "Inflammation Score" Beats "Bleeding Score"30:50 The Peak-End Rule: What Patients Actually Remember34:46 How to Ask Permission Before You Educate a Patient39:32 Scale and Polish vs Deep Clean: Explaining the Difference39:41 Midroll44:54 How to Introduce Full Mouth Rehab Without Overwhelming48:39 The Ladder of Readiness: Where Is Your Patient?55:02 Two Ladders: Clinical and Interpersonal Readiness59:23 How to Pre-Qualify Patients Before They Reach Your Chair1:11:32 How to Present a Five-Figure Treatment Plan1:20:26 OUTROCommunication course — waiting list: Zak has a communication course in preparation. Protrusive is supporting it with a 90-day accountability group inside the app for anyone who enrols, plus retained lifetime access to Loom School. The waiting list is at protrusive.co.uk/conversations.Find Zak Kara in Instagram (@zakdentalkitchen) and Facebook (Zak Kara).References & Further ReadingThe behavioural science referenced in this episode:Norton MI, Mochon D, Ariely D. The IKEA effect: When labor leads to love. Journal of Consumer Psychology, 2012;22(3):453–460. People value what they helped build — the mechanism underneath co-diagnosis.Bem DJ. Self-Perception Theory. Advances in Experimental Social Psychology, 1972;6:1–62. People infer what they believe partly from observing what they themselves say and do.Kahneman D, Fredrickson BL, Schreiber CA, Redelmeier DA. When more pain is preferred to less: Adding a better end. Psychological Science, 1993;4(6):401–405. The healthcare application is Redelmeier DA, Kahneman D, Patients’ memories of painful medical treatments, Pain, 1996;66(1):3–8.Want more?If you enjoyed this episode, check out: Think Comprehensive – Communication Gems with Zak Kara – PDP010. The episode that started it all.Tags#PDPMainEpisodes #CommunicationListen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 1.25 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes A.AGD Subject Code: 550 Practice Management and Human Relations.Aim & Learning OutcomesAim: To improve dental professionals’ ability to communicate the need for comprehensive or more extensive treatment to patients who present with single-tooth expectations, using structured, permission-based and goal-led conversation rather than persuasion.Learning Outcomes — by the end of this episode, dentists will be able to:Describe how a patient’s readiness for comprehensive treatment can be assessed along two parallel dimensions — their understanding of their own clinical need, and the strength of the working relationship — and identify where an individual patient sits on each.Apply permission-based and question-led techniques that help a patient identify disease for themselves, so that a recommendation is understood and owned rather than imposed.Dif...
-
 Studying Dentistry in Bulgaria / Spain / Hungary and Beyond - IC078 18.09.2026 55minEver wondered what it’s really like to study dentistry abroad?How different is it to train in Bulgaria, Slovakia, or Valencia compared to the UK?And what happens when it’s time to come back home — can you easily register with the GDC and start practicing?Dr. Hugo Medd joins Jaz for an honest and insightful conversation about taking the path less traveled — studying dentistry in Bulgaria after not securing a UK dental school place.They dive into the realities of living and learning abroad, including language barriers, different teaching styles, and how much clinical experience international students actually get. Hugo also shares how he navigated GDC registration, what it’s like finding work after graduation, and why he has no regrets about choosing this unconventional route.Highlight of this episode:00:00 TEASER01:21 Introduction02:49 Meet Dr. Hugo Medd: A Journey to Bulgaria06:09 Financial Considerations and Support Systems09:56 Why Bulgaria? DMD vs BDS explained13:13 Language Barriers and Communication Skill17:47 Tuition Fees, Cost of Living, and Financial Realities20:47 Navigating Post-Graduation and GDC Registration23:23 Accredited EU Universities and Recognition Rules25:09 Social Life, Culture, and Student Experience28:14 Midroll34:47 Differences in Teaching Styles Abroad40:54 Navigating the UK Dental Job Market43:03 Advice for New Graduates50:24 Pursuing a Master's in Oral Surgery54:45 Final Thoughts and Contact Information57:11 OUTROInspired to study abroad? Study Medicine Europe helps you land top dentistry and medicine placements in Europe and guides you from application to graduation.If you enjoyed this episode, check out “The American Dental Dream – PDP002”This episode is not eligible for CPD/CE points, but never fear, there are hundreds of hours of CPD waiting for you on the Ultimate Education Plan.#InterferenceCast #CareerDevelopment
-
 No More Air Polishing or Prophy Paste! Revolutionary New Technique for Non Mechanical Prophylaxis - PDP284 16.09.2026 59minHave you ever removed plaque using a scaler or ‘air-polisher’ and notice that the demineralised enamel flaked away?Scaling and polishing is a routine part of preventive dental care — but could some of our traditional cleaning methods be doing more than we realise? A whitening specialist who works without a drill, scaler or air polisher argues that some approaches to cleaning may affect the enamel, and that hydrogen peroxide gel can remove plaque without touching the tooth surface.Dr Wyman Chan has done nothing but tooth whitening since 2002, when he closed his general practice for a dedicated whitening centre, and he developed the chemical-polishing gel which is at the centre of this episode. He is joined by Dr Niki Shah, a UK general dentist and practice owner whose company distributes the product in the UK, and who now runs most of his hygiene this way.In this episode, they explain which patients they believe may benefit most, walk through the full chairside protocol, and discuss the limitations of the approach and where it may not be appropriate.Protrusive Dental Pearl: Manicuring Worn Lower IncisorsWorn lower incisors sit sharp against the upper teeth, concentrating stress. Take a Sof-Lex disc and manicure them, rounding the edges from pointed to smooth. Show the patient in the mirror first and, borrowing Dr Michael Melkers’ framing, ask if you can make their teeth look a little younger. It is surface topography, changed for force management, and the patient feels it with their tongue.What You’ll Take From This EpisodeOn sound enamel, prophy paste and air polishing are low-risk; on demineralised enamel hidden under plaque, the same abrasion can flake the surface.Chemical polishing does not lift calculus; where calculus is present, ultrasonic or hand scaling is still required.Dr. Wyman Chan offers a 3% hydrogen peroxide gel as a plaque and biofilm adjunct, not a replacement for oral hygiene instruction.The strongest cases for this are anxious, paediatric, orthodontic, special-needs and geriatric patients who tolerate scraping poorly.The chairside protocol runs about twelve minutes and still ends with manual agitation using a single-tufted brush.No published evidence supports the product’s clinical claims yet; Dr. Wyman Chan describes studies in progress.Highlights of This Episode00:00 Teaser01:21 Rethinking How We Polish Teeth03:36 Protrusive Dental Pearl: Manicuring Worn Lower Incisors05:23 Meet the Guests: From Whitening to Chemical Cleaning12:10 What Is Chemical Polishing? Prophylaxis, Not Whitening20:05 Is Traditional Polishing Damaging Teeth?21:54 How Abrasion Harms Demineralised Enamel25:30 The Strongest Case: Anxious Patients29:09 Children, Adolescents and Orthodontic White Spots29:49 Midroll35:22 Managing Pericoronitis and Gingival Abscess38:15 Special Needs, Geriatric and Post-Surgery Care40:43 Where Is the Evidence? Studies in Progress43:59 The Cost and Business Case for Chemical Polishing50:16 The Chemical Polishing Protocol: Step by Step using Magic353:14 Why Manual Agitation Still Matters57:58 How It Changed a Working Day1:00:35 OutroStart offering Magic3Where to get Magic3: UK: directoralcare.comRegister for a free professional account. Approval unlocks the full shop, pricing, offers and their upcoming educational courses.Use promo code PROMAGIC10 at checkout to receive 10% off Magic3.Outside UK: Please enquire from Dr Wyman Chan's website.Orders are invoiced rather than purchased directly through the website.Quote promo code PROMAGIC10 when enquiring to receive 10% off your Magic3 order.FREE Wyman Dental RetractorsWith your first Magic3 order, you’ll also receive 1 Wyman Dental Retractor free.The Wyman Dental Retractor is a multi-use, autoclavable retractor (up to 100 uses) designed for comfortable and effective soft-tissue retraction.Order 1–2 Magic3: Get 1 free Wyman Dental RetractorOrder 3+ Magic3: Get 3 free Wyman Dental RetractorsLearn more about their other products: https://protrusive.co.uk/magic3Want more?New to Dr Chan’s work? Start with Trayless Whitening Technique Part 1 with Dr Wyman Chan - PDP277, on his whitening approach, sensitivity and how to let patients pick their target shade.Tags#PDPMainEpisodesListen, subscribe, and earn CPDListen: Spotify, Apple Podcasts, YouTube, and inside Protrusive Guidance.Earn CPD: This episode is eligible for 1 CE credit via the quiz on Protrusive Guidance.Compliance: GDC Development Outcome C. AGD Subject Code 490 Periodontics.Aim & Learning OutcomesAim: To give a mechanism- and evidence-aware view of chemical polishing as an adjunct for plaque and biofilm removal: where mechanical polishing can harm demineralised enamel, which patients the approach suits, how the chairside protocol runs, and the limits of the current evidence.By the end of this episode, dentists will be able to:Describe how the abrasivity of prophylaxis pastes and air-polishing powders interacts with sound versus demineralised enamel.Identify the patient groups for whom a non-mechanical approach to plaque removal is most appropriate, and the situations, such as calculus, where it is not.Evaluate the current evidence base for a 3% hydrogen peroxide chemical-polishing protocol, and apply appropriate attribution and consent where the evidence is not established.
-
 Full Mouth Reconstruction with Lukasz Lassmann and Riaz Yar - PDP283 09.09.2026 1h 29minFull mouth reconstruction — is the aim really the flawless before-and-after you scroll past on Instagram, or is that a trap?How do you actually know you’re ready to step up from single teeth to a whole mouth?And when your comprehensive treatment plan keeps getting declined — psychologically, financially — is that the patient’s problem, or yours?This one is a “your questions answered” episode: the community sent in far more FMR questions than we could cover, and we put the best of them to two prosthodontists who literally wrote the book on it.This is a full-mouth reconstruction deep dive with Prof Riaz Yar and Dr Łukasz Lassmann — co-authors of the new Quintessence textbook Full-Mouth Reconstruction (foreword by Jeffrey Okeson). We cover screening before you commit, knowing when you’re ready, getting big plans accepted, choosing materials, setting the bite in centric relation, sleep apnea, and the honest truth about “perfect” versus “acceptable.”Protrusive Dental Pearl: Always Present the Best AdviceWhen you present a complex case, offer three tiers. Best advice — take time and money out of the equation and describe the ideal: what would truly get this patient to the right result (gum grafting, orthodontics, the lot). A compromise — a good result without the parts the patient won’t consent to or can’t fund. And the minimum — the least that still helps, with the non-negotiables named.The most important of the three is the best advice. It’s tempting to self-censor — to decide a plan is too elaborate or too expensive and quietly leave it out. But if you never present the best option, you’ll never get to do those cases. Present the ideal option first, then offer the compromises. Don’t limit the patient — or yourself.What You’ll Take From This EpisodeScreen before you plan — a green / orange / red system that sorts patients before treatment planning even starts, so you know which cases are yours.How to get big plans accepted — why case acceptance is a confidence problem before it’s a skills problem, and how to present the best advice, compromise and minimum.Choosing materials — why it’s the case, not the material: repairability vs aesthetics vs durability, and why erosion changes the answer.Setting the bite — why centric relation is the reference position, what a night guard can do to it, and how sleep apnea changes the plan.Perfect vs acceptable — defining success and failure honestly, and knowing when you’re actually ready to take a full-mouth on.Highlights of This Episode00:00 TEASER00:53 Full Mouth Reconstruction: Your FMR Questions Answered05:08 What Actually Counts as a Full Mouth Reconstruction?10:48 Screening Patients for Full Mouth Rehab: Green, Orange, Red18:48 Is Perfect the Goal of Every FMR? Success vs Failure26:53 How Do You Know You're Ready for Full Mouth Dentistry?36:23 Is the Dahl Concept a Good Segue Into Full Mouth Rehab?38:50 Midroll42:49 How to Get Patients to Accept Full Mouth Treatment Plans49:34 Best Advice, Compromise, Minimum: Presenting the Options55:04 Give Yourself Permission to Fail in Big Cases56:14 FMR or Selective Restorations? Where's the Line on Tooth Wear?58:49 interjection 11:04:52 Composite, Ceramic or Zirconia? Choosing FMR Materials1:09:53 interjection 21:12:40 Centric Relation, Sleep Apnea and Setting the Bite1:17:25 Anteriors or Posteriors First in a Full Mouth?1:26:00 Does DTR Change How You Finish an FMR?1:27:35 The Full-Mouth Reconstruction Book & Where to Learn More1:30:37 OUTROFrom the GuestsProf Riaz Yar is a specialist prosthodontist and Visiting Professor in Prosthodontics, with a 25-year focus on TMD, occlusion and full-mouth dentistry. Dr Łukasz Lassmann is a prosthodontist (DDS, PhD) whose PhD is in occlusion and the temporomandibular joint; he focuses on tooth wear, TMD and full-mouth rehab and founded Lassmann Education, whose multi-day “summer camp” FMR/occlusion course runs in Poland.Interested in Full Mouth Reconstruction? Check out their book: Full-Mouth Reconstruction (Lassmann & Yar, Quintessence Publishing, 2026; foreword by Jeffrey Okeson) — a general-practitioner workflow from screening through orthodontics, perio, preparation, and cementation. References & Further ReadingSources and further reading from this episode:Lassmann Ł, Yar R. Full-Mouth Reconstruction. Quintessence Publishing, 2026 (foreword by Jeffrey P. Okeson). ISBN 978-1-78698-153-0.Lassmann Ł, Calamita MA, Blatz MB. The “Smile Design and Space” (SDS) concept for altering vertical dimension of occlusion and esthetic restorative material selection. J Esthet Restor Dent. 2025;37(1):56–67.Loomans B, Opdam N, Attin T, et al. Severe tooth wear: European consensus statement on management guidelines. J Adhes Dent. 2017;19(2):111–119.Bartlett D, Ganss C, Lussi A. Basic Erosive Wear Examination (BEWE): a new scoring system for scientific and clinical needs. Clin Oral Investig. 2008;12(Suppl 1):S65–S68.Okeson JP. Management of Temporomandibular Disorders and Occlusion. Elsevier (8th edition) Want more?If you enjoyed this episode, check out: https://protrusive.app/posts/free-podcast-videos-pdp225-occlusion-myths-and-red-flags-with-lukasz-lassmannTags#PDPMainEpisodes #OcclusionTMDandSplints #OrthoRestorativeListen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 1.5 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes C.AGD Subject Code: 610 Fixed Prosthodontics.
-
 Daddy Dentist: Balancing Fatherhood and Dentistry - IC077 02.09.2026 58minWhen you walk through the door after work, are you actually present or are you still running the day’s to-do list in your head?Is there ever a “good” time to have a baby in the middle of specialist training and how do you fund it?How do the best dentist-parents you know protect time with their kids without their careers stalling?And can technology actually give you hours back — or is that just another thing to feel guilty about?This is one for the dads. In this Interference Cast episode, Jaz sits down with Dr Sunny Marwaha — a dentist completing part-time specialist training in prosthodontics at Guy’s, who became a father right in the middle of it. It’s not a clinical episode. It’s an honest conversation about doing the hardest career stretch (training, buying practices, building a name) at the exact same time you’re raising young children — the sleep, the money, the guilt, and the strategies that actually help. Two dentist dads, comparing notes.What You’ll Take From This EpisodePriority management, not time management — Decide what this season of life is for, and protect it; priorities shift as the kids grow.Leave the day at the door — both directions — The driveway is dad mode, the clinic is showtime; you can’t take work home or home to work.Run the family like a small business — Regular family meetings and a “mind like water” system can help carry the load without living in your head.Use AI to buy back time — Make use of dictated notes, auto-drafted letters, and turning papers into audio for the commute. This is leverage, not cheating.Specialise or self-direct? — An honest filter for whether a structured training pathway or private courses and mentorship suits you better.Highlights of This Episode00:00 Teaser00:42 Daddy Dentist: Balancing Fatherhood and Dentistry03:42 Should You Specialise or Learn Through Private Courses?10:12 How to Time Having Kids Around Specialist Training13:32 Paternity Leave for Dentists: What's Realistic?16:42 Funding Specialist Training With a Young Family20:02 Why Family Support Is a Privilege, Not a Given22:57 Time Management vs Priority Management23:42 The Two Moments With Your Kids That Matter Most29:12 Protecting Sleep, Fitness and Your Mental Health30:13 Midroll39:03 Top Tips for Dentist Dads41:53 Using AI to Buy Back Time for Your Family45:53 Run Your Family Like a Small Business53:33 How to Cut Kids' Screen Time (and Make It Stick)59:23 Life After Specialist Training: A Shorter Week59:57 OutroFrom the GuestDr Sunny Marwaha is a dentist completing part-time specialist training in prosthodontics at Guy’s (King’s College London). He’s passed the MProst (Royal College of Surgeons), with his final MClinDent and GDC specialist listing still ahead. He became a dad to son Kabir midway through training; his wife Amrit is also a dentist.👉 Follow Sunny on Instagram: @dr_marwahaReferences & Further ReadingListed for reference (mentions, not endorsements):NotebookLM — Google’s AI research tool; can turn a source document (e.g. a paper) into an audio, podcast-style discussion for the commute.Trello, Inkpad Notepad, and Google Calendar — The “mind like water” offload system. Loom — screen/video-message tool, mentioned as an alternative to written tooth-by-tooth reports.Want more?If you enjoyed this episode, check out: [Screen Times and SmartPhones for Children – Best Practices – IC061]. The screen-time reset comes up near the end of this chat; that episode goes deeper. Tags#InterferenceCast #CareerDevelopment #BeyondDentistryListen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 1.0 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcome B.AGD Subject Code: 770 Self-Improvement.
-
 The Art and Science of Complete Denture Success - PDP282 28.08.2026 55minComplete Dentures That Actually Work: Impressions, CR & AdaptationYou don’t have to suck at complete dentures — there’s a science to them, and an art you gather with experience.Why do complete dentures feel so unpredictable — when a crown prep or an endo doesn’t?What’s the number-one impression mistake dentists make — and the tissue-conditioning step most of us skip?And when a new denture comes back painful — is it the extension, or the occlusion?This one is a whistle-stop tour of complete dentures with Dr Leif Stromberg — a Dallas general dentist who learned removable prosthodontics directly from the legendary Earl Pound and has taught it for decades. Recently nominated for the Texas AGD’s 2026 Texas Dentist of the Year™ Award, Dr. Stromberg brings a wealth of clinical experience, leadership and mentorship to the profession.Rather than drilling into a single appointment, Jaz put a stack of Protrusive Guidance community questions to him and covered the whole arc, from choosing the right patient to troubleshooting a painful denture at delivery. Expect breadth over depth — a lot of ground, a little from each stage — with plenty of technique, nuance and communication tips to take back to the chair.Protrusive Dental Pearl: Pick the Patient Before the DentureYou don’t have to treat everyone. Before promising anything, work out whether you can meet the patient’s expectations — because you can build the world’s best denture and they still may not adapt to it. The single strongest predictor of success is the patient’s own adaptation, not the technical quality of the prosthesis.So read the markers of adaptation. The patient who has worn a technically poor, flimsy denture happily for years — and only needs a new one because the old one is worn out — is a home run: improve the retention and stability and they’ll do brilliantly, because their neuromuscular adaptation is already proven. The patient who has hated every set they’ve owned is the warning sign. Assess adaptation right from the first appointment; it matters more than the articulator you own.What You’ll Take From This EpisodePick the patient, not just the denture — the markers of adaptation that predict success before you start.Where the teeth actually go — Pound’s lingual control lines, and why “lingual” means stable.The number-one impression mistake — coverage versus overextension, plus pre-impression tissue conditioning.Records without the wobble — recording centric relation with a gothic arch tracer, and why the facebow ranks low.A painful denture at delivery — how to tell overextension from occlusal overload, and what to do about each.Highlights of This EpisodeFrom the GuestDr. Stromberg teaches the fundamentals of predictable complete dentures through a run of CE courses on Dentaltown — a five-part written series and a video series that walk through the exam, impressions, records, try-in and delivery.👉 Stromberg’s “Keys to Complete Denture Success” CE courses on DentaltownLearn more at: https://www.strombergdentistry.com/articlesWant more?If you enjoyed this episode, check out: Occlusion for Complete Dentures – PDP162Tags#PDPMainEpisodes #ProsthoPerio #Communication Listen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 0.75 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes CAGD Subject Code: 670 Removable Prosthodontics.Aim & Learning OutcomesAim: To give clinicians a predictable, appointment-by-appointment approach to complete dentures — patient selection and adaptation, accurate records, functional tooth position, and troubleshooting at delivery.Learning Outcomes — by the end of this episode, dentists will be able to:1. Assess a patient’s suitability for complete dentures and their likely adaptation, and manage expectations before treatment begins.2. Describe the sequence of clinical appointments for complete dentures and the key objective of each — impression coverage, recording centric relation and vertical dimension, and functional tooth position.3. Differentiate the common causes of pain at denture delivery (overextension versus occlusal overload) and apply an appropriate method to identify and correct each.
-
 Biological Dentistry vs Holistic - Trend or Future? Implementing Nutrition and Testing - PDP281 26.08.2026 57minHolistic, biological, functional — is there actually a difference, or is it all just marketing?Are root canals really dangerous — or is that just what the algorithm keeps showing your patients?When a patient wants their sound fillings out, do you test, reassure, or drill?And how do you bring sleep, diet and blood tests into a dental appointment without it stopping being dentistry?This episode sits down with Dr James Goolnik (https://uk.linkedin.com/in/james-goolnik)— clinical dentist, founder of the London holistic practice Optimal Dental Health, past President of the British Academy of Cosmetic Dentistry, and one of Jaz’s earliest mentors. James openly calls himself a holistic and biological dentist, which makes him the ideal person to separate the thoughtful, evidence-aware end of this world from the online extremism that gives it a bad name. Expect a balanced, honest conversation: some of it you’ll adopt tomorrow, some of it you’ll want to pressure-test — which is exactly the point.Protrusive Dental Pearl: Dentistry Isn’t Just About Fixing TeethThis one isn’t a clinical tip — it’s a sentiment that frames the whole episode. Dentistry isn’t just about fixing teeth; it’s about improving health. You don’t have to agree with every claim made in biological dentistry — but you will struggle to disagree that a patient’s diet, sleep, breathing, stress and inflammation all influence oral health.So the pearl is simple: stay curious, stay open-minded — but stay critical, and never stop asking better questions.What You’ll Take From This EpisodeThe holistic–biological spectrum — what each word actually means, and where thoughtful practice tips into online extremism.Test or reassure? — the three-question filter for deciding whether any test earns its place before you order it.Safe amalgam removal — the SMART protocol, and when a worried patient’s sound filling should be left well alone.The mouth-body connection — how sleep, glucose control and systemic inflammation affect the mouth, and where to refer.The balanced take on root canals and implants — whether root canals are dangerous, and titanium versus ceramic with metal-allergy testing.Highlights of This Episode00:00 Teaser00:59 Holistic vs Biological Dentistry: What's the Difference?05:49 Why Listening Beats Perfect Margins in Dentistry10:29 Why Patients Started to Doubt Root Canal Treatment12:09 Mercury Fillings: Should You Remove Amalgam?14:09 The SMART Protocol for Safe Amalgam Removal19:59 The Mouth-Body Connection: Sleep, Diabetes & Alzheimer's24:59 How to Build Nutrition Into a Dental Practice26:25 Midroll34:01 Sleep Tests, Glucose Monitors and Blood Tests in Practice38:21 Is Biological Dentistry Dangerous? The Extremist Problem39:21 Are Root Canals Dangerous? A Balanced Take41:51 Titanium vs Zirconia Implants and Metal Allergy Testing46:51 When Removing a Healthy Tooth Becomes Negligent50:56 What Diet Should Dentists Actually Follow?53:41 How to Get Started in Holistic Dentistry56:30 OutroFrom the GuestDr James Goolnik is a clinical dentist and founder of Optimal Dental Health, a holistic practice in London built around integrating nutrition, sleep and whole-health screening into everyday dentistry. He is a past President of the British Academy of Cosmetic Dentistry, a member of the International Academy of Oral Medicine and Toxicology, and the author of “Brush” (profits to Dentaid) and the “Kick Sugar” cookbook (profits to his Rewards Project charity).👉 Optimal Dental Health — monthly practitioner newsletter, and connect with James on LinkedInWant the Toolkit?We’ve turned this episode into a practical Holistic Dentistry Clinical Toolkit — with quick-reference guides for whole-body assessment, testing, patient conversations, and navigating the holistic–biological spectrum.Download the free toolkit at www.protrusive.co.uk/biologicalReferences & Further ReadingSources and further reading from this episode:IAOMT — Safe Mercury Amalgam Removal Technique (SMART). The protocol for safely removing amalgam (rubber-dam isolation, adsorbent rinse, sectioning, high-volume evacuation) to minimise mercury exposure for patient and team. MELISA test. A validated blood lymphocyte-transformation test for type-IV hypersensitivity to metals including titanium and mercury — used to guide titanium-vs-ceramic implant decisions. Tests, devices & materials referenced — a home overnight sleep test, a phase-contrast microscope, a national blood-testing partner, point-of-care fingerprick analysers (CRP / HbA1c), a blood/hair/urine mercury panel, continuous glucose monitors, and Biodentine for vital-pulp therapy. Want more?If you enjoyed this episode, check out: Implementing Sleep, Airway and Myo to Restorative Dentistry Part 1 — PDP262Tags#PDPMainEpisodes #Communication #BeyondDentistryListen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 1.0 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes C.AGD Subject Code: 150 Health, medicine and nutrition.Aim & Learning OutcomesAim: To give dentists a balanced, evidence-aware understanding of holistic and biological dentistry — what the terms mean, how to integrate whole-health thinking and appropriate testing into practice, and how to navigate patient beliefs about root canals, mercury and metal-free dentistry without abandoning the evidence base.Learning Outcomes — by the end of this episode, dentists will be able to:1. Differentiate between holistic and biological approaches to dentistry, and articulate where evidence-based, minimally invasive care ends and unsupported claims begin.2. Apply a structured decision filter to judge whether an additional test or intervention is justified — whether it will change treatment, provide a benchmark, or motivate the patient — while working within scope and referring appropriately.3. Describe t...
-
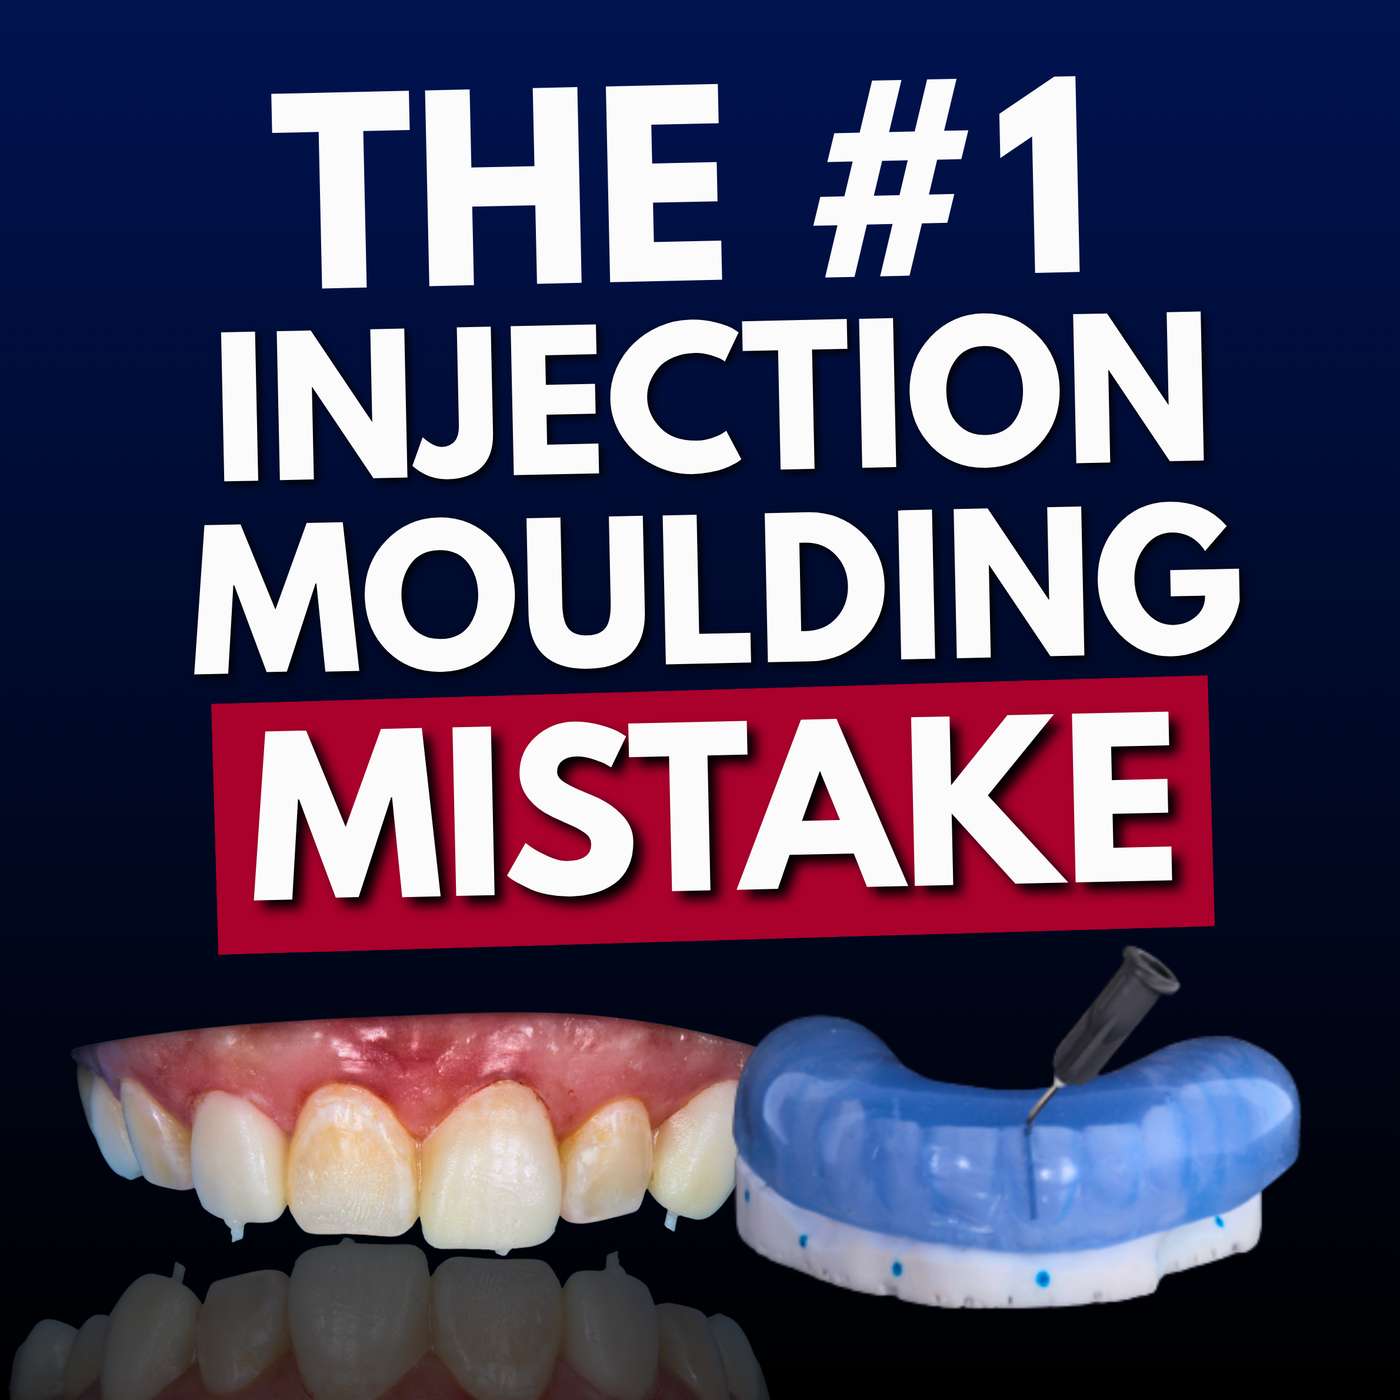 How Not to Cry Whilst Injection Moulding - Secrets to Reduce Excess and Clean Up - PDP280 19.08.2026 48minInjection moulding is meant to save you time. Too often it hands you a mouthful of flash and a cleanup that swallows the chair time you thought you were saving.Dr Sandra Hulac is a Clinical Instructor at the Kois Center in Seattle and an Accredited Fellow of the American Academy of Cosmetic Dentistry. She uses full-mouth injection moulding to road-test occlusions and stabilise breaking-down dentitions, and she teaches the technique hands-on.In this episode she works through where the mess actually comes from, and how design, matrix strategy, careful PTFE and a simple cleanup protocol keep a case clean from the first injection.This episode comes with an infographic: the whole no-mess workflow on one visual guide to keep beside you during design and cleanup. Download it at protrusive.co.uk/nomess. It is the fastest way to turn this episode into something you actually use at the chair.What You’ll Take From This EpisodeMost injection-moulding mess is prevented at the design stage, through thickness targets and clear lab communication, long before any cleanup.The alternating matrix technique, injecting every other tooth, is the biggest single cleanup saver and cuts the PTFE you need.Matrices cured in a pressure pot, with a spacer protocol, give even thickness and far fewer bubbles.Thin, careful PTFE prevents distortion; bunching it interproximally creates the very excess you are trying to avoid.An S-shaped motion with a Ceri-saw and several 12-plate blades clears resin while protecting the contact.Good pre-treatment hygiene, using diluted hypochlorite or povidone-iodine rather than chlorhexidine, cuts bleeding and contamination.Highlights of this episode:00:00 Teaser00:54 Introduction02:17 Dental Pearl: Free Injection Moulding Infographic03:17 Main Interview with Dr. Sandra Hulac4:49 Innovations in Dental Education07:26 The Mess Problem in Injection Moulding15:38 Alternating Matrix Technique18:18 Every-Other-Tooth Technique27:54 Cleanup Instruments and Techniques31:35 Handling Teflon and PTFE36:41 Patient Oral Hygiene Tips37:27 Dilution protocol:39:24 Key Principles for Minimizing Mess40:42 Matrix Fabrication and Spacer Protocol43:55 Course Information and Conclusion46:19 OutroFrom the GuestMaster Full Mouth Injection Moulding in this exclusive two-day hands-on course!📅 Dates: Feb. 26-27, 2027📍 Location: Central London Venue (TBC)🌐 Learn more & secure your spot: protrusive.co.uk/FMIMWant more?Learn to treat tooth wear with injectable composite in Injectable Composites in PDP081Tags#PDPMainEpisodes, #BreadandButterDentistry, #AdhesiveDentistryListen, subscribe, and earn CPDListen: Spotify, Apple Podcasts, YouTube, and inside Protrusive Guidance.Earn CPD: This episode is eligible for 0.75 CE credit via the quiz on Protrusive Guidance.Compliance: GDC Development Outcome C. AGD Subject Code 250 Operative (Restorative) Dentistry.Aim & Learning OutcomesAim: To enable dental professionals to minimise cleanup during injection moulding by optimising design, matrix use, PTFE application, and interproximal finishing techniques.By the end of this episode, dentists will be able to:Explain how proper design and lab communication can reduce composite flash and cleanup in injection moulding.Demonstrate the alternating matrix technique and the correct use of PTFE in minimising mess.Identify and use appropriate instruments and techniques for efficient interproximal cleanup after injection moulding.
-
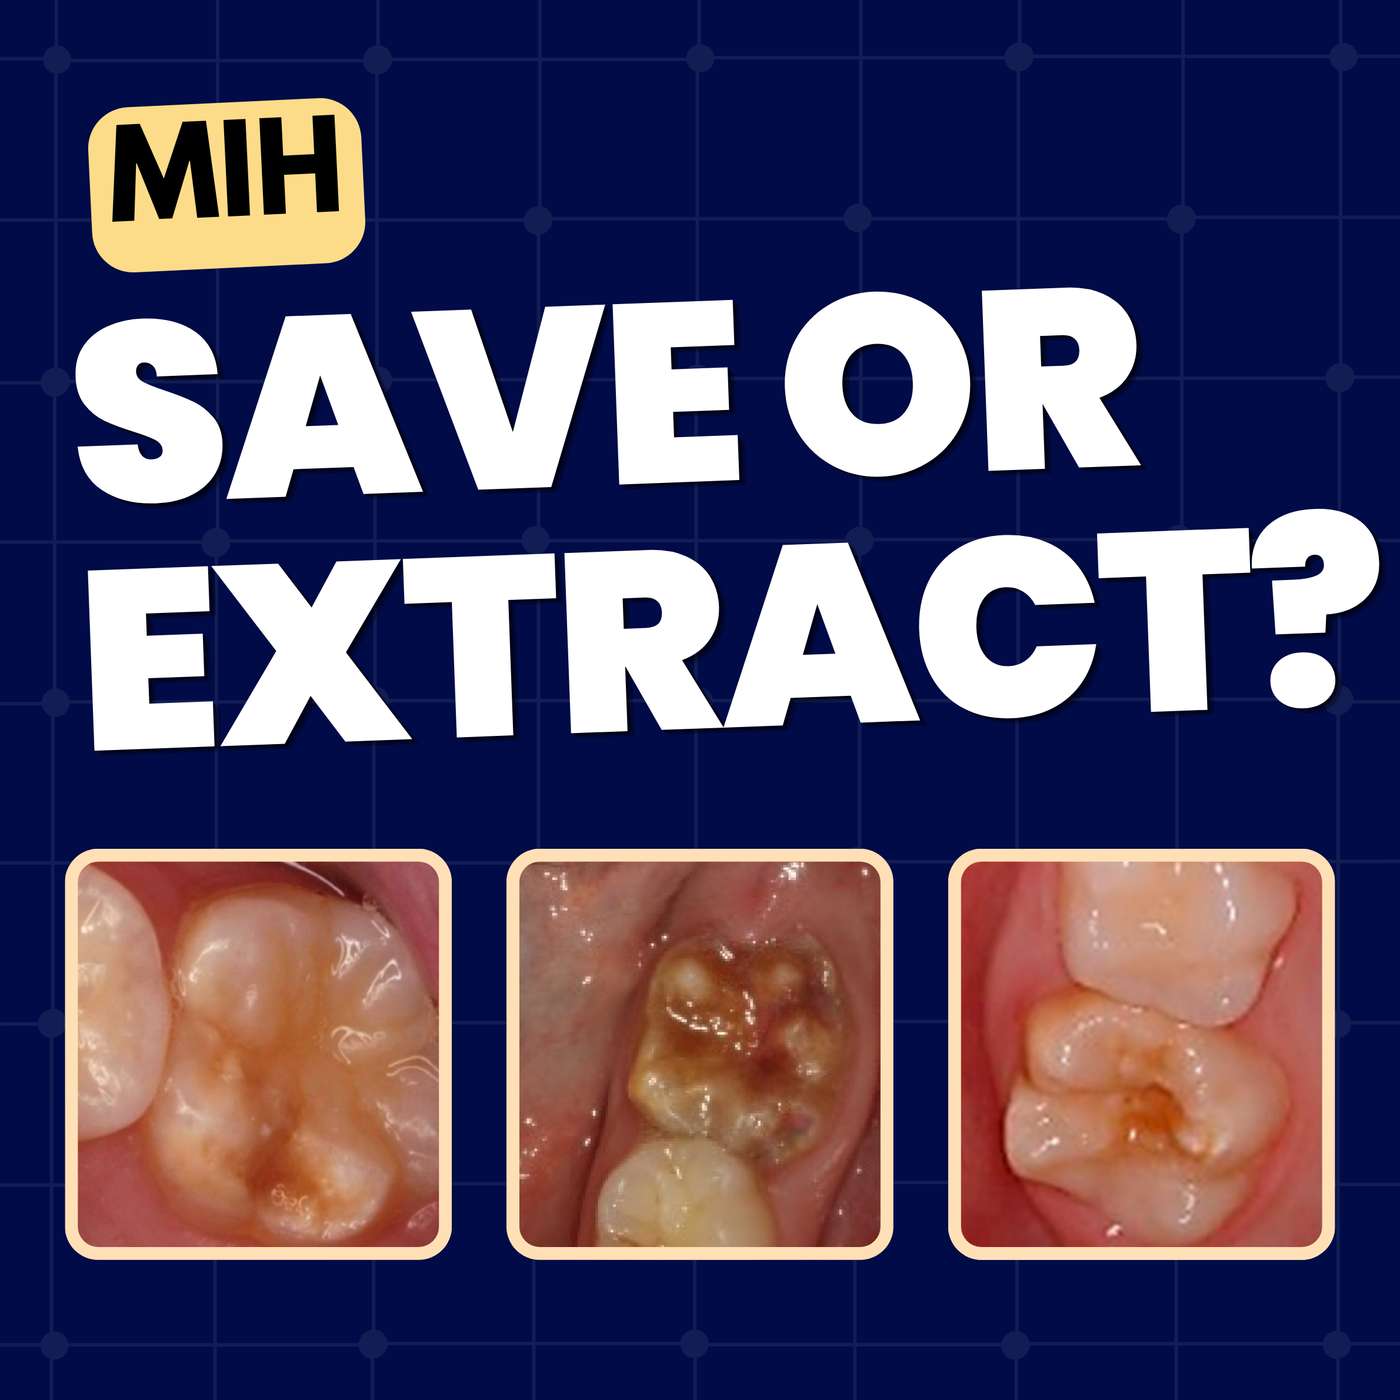 Maintain or Extract? First Permanent Molars of Poor Prognosis - PDP279 12.08.2026 53minYour patient is nine years old. One first permanent molar is crumbling — the others look fine. Does it stay, or does it go?Is that broken-down first permanent molar really down to poor brushing — or is it Molar Incisor Hypomineralisation?When is the right time to take a first permanent molar out — and how do you read it off the X-ray?And how do you tell a parent their child needs an adult tooth removed — without losing them?First permanent molars of poor prognosis are one of the genuine head-scratchers of general practice — full of ifs, buts and timing. In this episode Jaz sits down with Dr Nicole Sturzenbaum, a paediatric dentist and the owner and clinical director of Toothbeary in Richmond, London, to work through the whole decision: getting the diagnosis right (molar-incisor hypomineralisation versus caries), reading the extraction window off an OPG, the restorative ladder from sealant to stainless steel crown, when to bring in the orthodontist, and how to handle the conversation with anxious parents. There’s no one-size-fits-all answer — but there is a clear way to think about it.Protrusive Dental Pearl: Painless Polishing for Anxious KidsThe mechanical clean is what frightens children (and plenty of adults) — the scaler, the bristle brush, the gritty prophy paste. For the polishing part, a colourless plaque-dissolving foam gel does the job without any of it. It fizzes wherever there is plaque, so you can hand the child a mirror and show them exactly where to brush; it leaves the teeth satin-smooth, reduces gingival inflammation, and is painless and non-invasive.Two caveats: it does not remove calculus — you still need a hand or ultrasonic scaler for that — and you should agitate the gel gently at the gingival margin for the full effect. It is especially useful for orthodontic and adolescent patients because it reaches the nooks around brackets, which is where post-orthodontic white-spot lesions start.Product: Magic3 (3% hydrogen peroxide, colourless plaque indicator), by Dr Wyman Chan — protrusive.co.uk/magic3.What You’ll Take From This EpisodeDiagnosis first — MIH or caries? The distinction changes the plan, the prognosis and the whole conversation with the family.Reading the extraction window off an OPG — why chronological age tells you nothing, and what the second molar’s bifurcation tells you instead.The restorative ladder — seal, composite, preformed metal crown, or plan the extraction: matching the least invasive option that will actually hold.When to involve the orthodontist — essential or desirable, which teeth come out, and managing the space afterwards.Getting sensitive molars numb — why MIH teeth are so hard to anaesthetise, and the comfort stack that helps.Highlights of This Episode00:00 TEASER00:59 First Permanent Molars of Poor Prognosis in Children02:51 Painless Chemical Polishing for Kids (Protrusive Dental Pearl)04:53 Meet Dr Nicole Sturzenbaum, Paediatric Dentist11:49 MIH or Caries? Getting the Diagnosis Right15:14 What Is MIH? Causes, Grades and 'Cheese Molars'17:23 When to Extract a First Molar: Reading the OPG20:08 Sealant, Composite or Crown for MIH Molars22:32 Stainless Steel Crowns for Hypomineralised Molars25:52 Do You Need an Orthodontic Opinion Before Extraction?29:15 Talking to Parents About Removing an Adult Tooth31:56 Anaesthesia Tips for Sensitive MIH Molars36:14 Managing the Space After First Molar Extraction41:15 Balancing and Compensating Extractions Explained47:53 Early Orthodontics and Prevention at Toothbeary51:15 OUTROFrom the GuestDr Nicole Sturzenbaum is a paediatric dentist and the owner and clinical director of Toothbeary, a paediatric dental practice in Richmond, London. 👉 Toothbeary — paediatric dentistry, sedation & early orthodontics, Richmond, LondonReferences & Further ReadingEAPD guidance (cited on the episode). European Academy of Paediatric Dentistry policy documents on MIH (Lygidakis et al., best clinical practice guidance for clinicians dealing with children presenting with MIH) and on paediatric local analgesia (Kühnisch et al., 2017).Preoperative analgesia for MIH (further reading). Vicioni-Marques, F., Paula-Silva, F. W. G., Carvalho, M. R., Queiroz, A. M., Freitas, O., Duarte, M. P. F., Manton, D. J., & Carvalho, F. K. (2022). Preemptive analgesia with ibuprofen increases anesthetic efficacy in children with severe molar: a triple-blind randomized clinical trial. Journal of applied oral science : revista FOB, 30, e20210538. https://doi.org/10.1590/1678-7757-2021-0538Want more?If you enjoyed this episode, check out: Zirconia vs Metal Hall Crowns vs Conventional with Dr Tim Keys – PDP227Tags#PDPMainEpisodes #OrthoRestorativeListen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 1.0 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes C.AGD Subject Code: 430 Pediatric Dentistry.Aim & Learning OutcomesAim: To help general dentists diagnose, assess and manage first permanent molars of poor prognosis in children — recognising molar-incisor hypomineralisation, timing extraction from radiographic development, and choosing between restoration and extraction with the wider team.Learning Outcomes — by the end of this episode, dentists will be able to:Differentiate molar-incisor hypomineralisation from caries of hygiene origin, and explain how that distinction changes management and communication.Apply radiographic developmental assessment — the second molar’s bifurcation and the presence of third molars — to judge the timing of first permanent molar extraction.Select an appropriate management pathway, from sealant and composite through preformed metal crown...
-
 TRAYLESS Whitening Technique Part 2 - Tetracycline Staining and Non Vital Bleaching Scenario! - PDP278 05.08.2026 1h 2minPatient has patchy white spots after braces — do you really whiten, or will that just make the spots stand out more?Tetracycline staining darker than your darkest shade tab — is bleaching even worth attempting, or is it veneers by default?A single dark, root-filled central incisor — can you fix it without picking up a drill at all?And how do you talk a patient through weeks, shades and cost so they actually consent to the slow, non-invasive route?This is Part 2 of the trayless whitening series with Dr Wyman Chan — inventor of trayless teeth whitening and the Get2Smile system — and Dr Elvis Law, who now runs around 90% of his whitening trayless. Part 1 covered the science and the everyday protocol; this part applies it to the three cases dentists find hardest, with the costing and consent conversations that make them work.Protrusive Dental Pearl: Treating Family and FriendsAlmost every clinician has a story about a case that went wrong on a family member, a friend, or a loved one. It’s not a random fluke. When we treat someone we love, we put our guard down — we relax the checklist, skip a step, get driven by emotion, and lose our judgement.So if you must treat family and friends, stay razor-sharp and treat them exactly as you would a stranger. Be extra vigilant, extra hot on your protocols, and take the emotion out of it. If that tooth needs a root canal, it needs a root canal — don’t bend the plan to preserve pulp vitality that was never the right call. The best pearl is not to treat loved ones at all; the real-world one is to not lose your judgement when you do.What You’ll Take From This EpisodeThe frosted glass model — a patient-ready way to explain white spots: enamel is clear glass, dentine is a yellow sponge, and acid has turned the glass frosty.A two-stage white spot protocol — remineralise and condition the gums first, then whiten trayless, and why a dirty tray would have sabotaged the result.Whitening tetracycline staining — realistic timelines, why darker teeth lift faster, and how to frame it honestly against veneers.The non-vital tooth without a drill — whiten every tooth to target, then paint the single dark tooth to match, and why leakage (not the bleach) causes rebound.Costing and consent — charging “almost by time,” staged reviews, and matching invasiveness to the mouth in front of you.Highlights of This Episode00:00 Teaser01:05 Trayless Whitening Part 2: Recap of Part 103:55 Protrusive Dental Pearl: Treating Family and Friends06:55 Whitening White Spot Lesions After Orthodontics11:55 Whiten First or Restore First? Cavitated Anterior Caries18:35 The Frosted Glass Analogy: Explaining White Spots to Patients21:05 A Two-Stage White Spot Protocol: Remineralise, Then Whiten32:57 Midroll36:23 Whitening Tetracycline-Stained Teeth40:03 Costing and Consent: Bleaching vs Veneers46:23 Whitening a Non-Vital Yellow Central Incisor47:43 Why Root-Filled Teeth Rebound After Bleaching53:13 Trayless Single-Tooth Whitening Without a Drill1:00:43 How to Access Trayless Whitening and Training1:03:40 OutroFrom the GuestDr Wyman Chan is the inventor of trayless teeth whitening and the Get2Smile system, with a PhD in the efficacy and safety of teeth whitening and a whitening clinic in London’s West End. Dr Elvis Law trained in safe dental bleaching under Dr Wyman Chan and now runs the majority of his whitening trayless.Start Offering Trayless Whitening for Your OfficeUK Dentists:In the UK you need the Get2Smile Kit which is 6% formulation applied twice daily for 30 minutes.Head to directoralcare.com and register for a free professional account. Approval unlocks the full shop, pricing, offers and their upcoming educational courses.At checkout, use code: DOCSUMMER20International Dentists wishing to offer Get2Smile, please enquire from Dr Chan's website. The international version uses 10% formulation applied for 15 minutes, twice daily.📌 Want to learn directly from Dr Wyman Chan? Join him for Redefining Early Caries Management and Aesthetic Dentistry in Shanghai, China, on 20–21 October 2026.Saturday 5th September London, UK CPD EVENT:👉Join Dr Wyman Chan for an exciting event focused on redefining the management of dental plaque-induced oral diseases.📍 Royal Asiatic Society, London NW1 2HDThe session will include a live lecture, clinical demonstration, and the opportunity to take part in practical, hands-on training. Dr Wyman Chan will be joined by Dr Niki Shah and Dr Elvis Law, who will also showcase their clinical cases.Want more?If you enjoyed this episode, check out: MAGIC Teeth Whitening with Dr. Wyman Chan – PDP245 — Wyman’s first Protrusive episode, covering whitening myths, sensitivity, and whether in-office lights do anything at all..Tags#PDPMainEpisodesListen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 1 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes CAGD Subject Code: 780 Esthetics/Cosmetic Dentistry.Aim & Learning OutcomesAim: To give dental practitioners a practical, non-invasive approach to three difficult whitening presentations — post-orthodontic white spot lesions, tetracycline staining, and a discoloured non-vital tooth — together with the expectation-setting and consent conversations that make treatment succeed.Learning Outcomes — by the end of this episode, dentists will be able to:Describe how enamel demineralisation produces white spot lesions and explain, in patient-friendly terms, why a repair-then-whiten sequence addresses both the surface and the underlying tooth colour.Apply a staged, non-invasive protocol to manage white spot, tetracycline and non-vital discolouration cases, selecting an appropriate route by matching invasiveness to the individual patient.Articulate realistic expectations on shade, timeline and cost, and use them to obtain informed consent for an extended, reviewable whitening course.
-
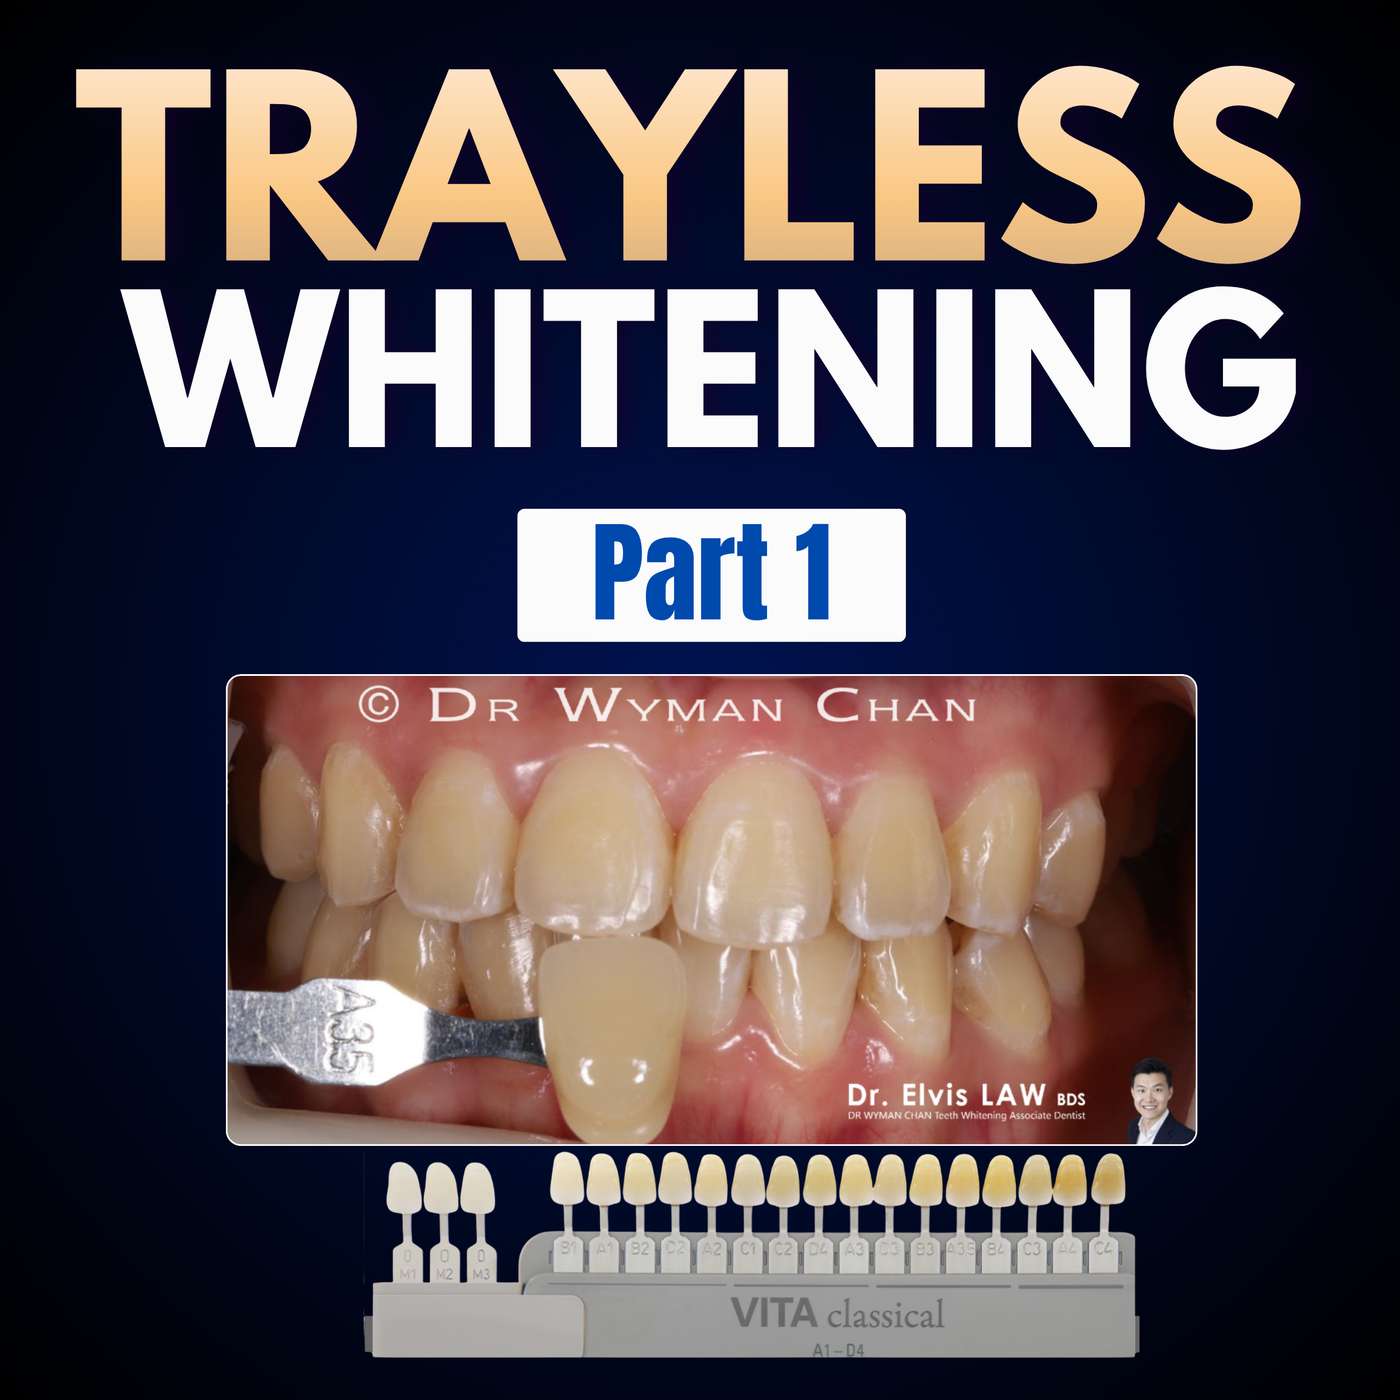 TRAYLESS Whitening Technique Part 1 - with Dr Wyman Chan - PDP277 30.07.2026 1h 6minWhat if the tray is the reason your whitening results are inconsistent?Why would a dentist who owns a whitening lab — and holds four patents on making bleaching trays — tell you to skip the tray?Trayless whitening does not mean strips. It means the patient puts in a retractor and paints the gel directly onto the teeth, twice a day, for half an hour. No impression, no lab bill, no two-week wait, and no soft plastic reservoir quietly absorbing your peroxide.This is Part 1 of a two-part conversation with Dr Wyman Chanand Dr Elvis Law, recorded live in their central London whitening practice. Wyman has done nothing but whitening since 2002, has a PhD on the efficacy and safety of whitening processes, and — despite owning the lab that makes the trays — now does most of his cases without one. Elvis trained under him and reckons around 90% of his own cases are now trayless.Part 1 is the mechanism, the protocol and an honest list of who it doesn’t suit. Part 2 takes it into the hard cases.Protrusive Dental Pearl: Let the Patient Pick the ShadeMost of us ask “how white do you want to go?”, get a laugh about Hollywood white or Simon Cowell white, then hold a B1 tab against the canine and call that the destination. Try flipping it.Under corrected light, record where the patient is now. Then hand over the whole shade guide, arranged by value, and let them choose the tab they want to reach. Photograph both.This is the VITA Shade guide arranged by value:B1 → A1 → B2 → D2 → A2 → C1 → C2 → D4 → A3 → D3 → B3 → A3.5 → B4 → C3 → A4 → C4Two things change. You now know the target precisely instead of inferring it, and you can track progress against a fixed reference. Most patients land on B1 — it’s the last shade before the bleach range, and it reads natural rather than veneered. Some will point at 0M1 and that’s a different conversation, which is exactly the point.Because whatever they choose dictates how many weeks, how much gel and how many reviews the case needs — and therefore what it should cost. A single flat whitening fee assumes every case takes the same work. They don’t. Someone starting at C4 who wants a bleach shade can get there, but it takes more gel, more time, more reviews and probably a protocol change along the way. Price that honestly.Only you can decide what the tiers look like in your practice. But it might be worth sitting down as a team of dentists and therapists and asking: how are we delivering whitening? Two tiers? More? Based on what?What You’ll Take From This EpisodeConscious bleaching — why an awake patient with an open mouth is a completely different chemical situation to a sealed tray worn overnight, and what that does to sensitivity.The formulation constraint — peroxide needs acid to stay stable on the shelf, which is why pre-mixed products lean acidic and why two-component gels exist at all.The full trayless protocol — wear schedule, spacing, patient positioning, review intervals and what to troubleshoot first when a case is behind.Who it doesn’t suit — an honest contraindications list, including the one objection patients raise most often and the answer to it.Tray hygiene as a clinical instruction — the reason results vary so much between patients using the identical gel.An A3.5 to B1 case — start to finish in three weeks, with the review points and the maintenance plan.Highlights of This Episode00:00 TEASER01:05 Trayless Teeth Whitening Explained03:40 Protrusive Dental Pearl: Let Patients Pick Their Whitening Shade06:05 Meet the Guests: A Career Built on Teeth Whitening10:27 What Is Trayless Whitening? (It's Not Whitening Strips)13:44 Why Whitening Trays Waste Your Bleaching Gel15:37 Are Whitening Strips Acidic? Gel Formulation Explained19:17 Conscious Bleaching and Whitening Sensitivity24:43 When NOT to Use Trayless Whitening29:05 The Trayless Whitening Protocol: 30 Minutes Twice a Day32:55 Midroll42:45 How to Clean Whitening Trays Properly50:02 A3.5 to B1 in Three Weeks: A Case Walkthrough56:16 Tooth Porosity and the 45-Degree Recline Rule1:02:09 Whitening Top-Ups and the Five-Year Guarantee1:06:49 How to Price Teeth Whitening and Let Patients Pick the Shade1:07:45 OUTRO1:12:56 What's Coming in Part 2Start Offering Trayless Whitening for Your OfficeUK Dentists:In the UK you need the Get2Smile Kit which is 6% formulation applied twice daily for 30 minutes.Head to directoralcare.com and register for a free professional account. Approval unlocks the full shop, pricing, offers and their upcoming educational courses.At checkout, use code: DOCSUMMER20The Trayless whitening system is called Get2Smile.International Dentists wishing to offer Get2Smile, please enquire from Dr Chan's website. The international version uses 10% formulation applied for 15 minutes, twice daily.📌 Want to learn directly from Dr Wyman Chan? Join him for Redefining Early Caries Management and Aesthetic Dentistry in Shanghai, China, on 20–21 October 2026.Join Dr Wyman Chan for an exciting event focused on redefining the management of dental plaque-induced oral diseases.The session will include a live lecture, clinical demonstration, and the opportunity to take part in practical, hands-on training. Dr Wyman Chan will be joined by Dr Niki Shah and Dr Elvis Law, who will also showcase their clinical cases.Want more?If you enjoyed this episode, check out: MAGIC Teeth Whitening with Dr. Wyman Chan – PDP245 — Wyman’s first Protrusive episode, covering whitening myths, sensitivity, and whether in-office lights do anything at all.Tags#PDPMainEpisodes Listen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 1 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes C.AGD Subject Code: 780 Esthetics/Cosmetic Dentis...
-
 What Dental School Didn’t Prepare You For – PDP276 22.07.2026 46minJust qualified — so why does it feel like the learning is only just beginning?What should you actually focus on in year one: the flawless dentistry on your feed, or something far less glamorous?How do you tell a patient their nerve might die — without it sounding like YOUR fault?And when a patient says “just do whatever you think” — what do you say back?This is the conversation every new dentist needs and every experienced one recognises. Our guest is Dr Emma Hutchison — a former dental nurse who trained at the University of Glasgow, and has been the face of the Protrusive Students series across her studies. We recorded in her final weeks of dental school, right on the threshold of practice, and talked through everything the syllabus skips: the safe-beginner mindset, what to learn (and what to ignore) early on, how to protect your standards under time pressure, which cases to take on, and how to talk to patients about risk, cost and consent so the words actually land. If you’re fresh out, this one hits hard. If you’re an oldie, it’s a trip down memory lane — and a reminder of how far you’ve come. https://youtu.be/gjJiDVP4w-4 Watch PDP276 on YouTubeProtrusive Dental Pearl: Predict the Complication Before It HappensA communication pearl for every deep restoration. When a filling sits close to the nerve — a big cavity, a crack — name the likely complication before it happens. Show the patient the images, then tell them what to expect: a twinge to cold or hot that can linger a few days, so keep taking painkillers and keep the area clean. And warn them what a red flag looks like: a severe throbbing ache keeping them up at night, or pain out of the blue without eating or drinking, means the nerve is struggling and they should call you.Do this and, if the complication ever arrives, you look like the expert who called it — not someone something went wrong for. Skip it and reception fields the panicked calls instead. It reassures the patient, lowers your callback rate, and quietly reduces your risk profile. Obvious, easy to forget, and worth saying out loud every single time.What You’ll Take From This EpisodeThe safe-beginner mindset — why qualifying is the driving licence, not the destination, and how the happiest dentists keep getting 1% better.Just-in-time learning — study for the cases actually in your diary, not the obscure pathology you won’t meet for years.Get good before you get fast — master the bread and butter, protect a little extra time early, and reflect on every procedure.Clever hacks vs cutting corners — how to tell the difference, and why every shortcut quietly rewires the habit.Consent that works — getting patients to own the problem, and giving a clear recommendation instead of a fifteen-item menu.Highlights of This Episode00:00 Teaser01:05 The Things Dental School Doesn’t Prepare You For03:05 Communication Pearl: Predict the Complication Before It Happens05:35 Life as a Final-Year Dental Student on Outreach09:55 Why You’re Only a “Safe Beginner” When You Qualify13:45 Master Bread-and-Butter Dentistry Before the Fancy Stuff16:05 Just-in-Time Learning: Study for the Cases in Front of You18:05 Get Good Before You Get Fast (and Protect Your Time)19:45 Clever Hacks vs Cutting Corners: Don’t Lose Your Standards24:14 Midroll27:46 The Skills to Nail in Your First Year as a Dentist30:11 Which Cases to Take On — and Learning From Mistakes35:46 How to Explain Risk and Get Patients to Own the Problem41:26 When Patients Refuse the Ideal Treatment: Start With Their Goal44:26 Treatment Planning Without the Overwhelm: Loom & “Guess Who”47:36 Claim Your CPD & Become the Next Protrusive Student47:38 OutroDr Emma Hutchison came to dentistry the long way round — from a dental nursing background into dental school at the University of Glasgow, with final-year outreach on the Kintyre peninsula in Campbeltown. She has been the face of the Protrusive Students series throughout her studies, and this episode marks her crossing from student to newly qualified dentist. On behalf of the whole Protruserati: we’re proud of you, Emma.Become the next Protrusive Student: with Emma qualifying, we’re looking for the next keen student who wants part-time work, an income while studying, and to contribute to Protrusive — or a nudge if you know one. DM the team inside the Protrusive Guidance app.Resources & Mentions From This EpisodeQuick & slick rubber dam — the in-app video series on quadrant isolation, for building the rubber dam habit from day one.21-Day Photography Challenge — the in-app challenge that walks you through capturing every clinical photo, including the dreaded occlusal shots, in your first three weeks.Loom School — in-app training on async, Loom-video treatment planning (roughly 90 minutes of CPD across around 15 bite-sized lessons).Access the above masterclasses and more when you subscribe to the Ultimate or Infinity plan.Want more?If you enjoyed this episode, check out: Periodontics for Beginners – PS008#PDPMainEpisodes #CareerDevelopment #Communication Listen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 0.5 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes A and D.AGD Subject Code: 770 Self-Improvement Aim & Learning OutcomesAim: To give early-career dentists a practical framework for the transition from dental school to independent practice — how to keep developing, how to protect clinical standards under time pressure, and how to communicate risk and treatment options as part of valid consent.Learning Outcomes — by the end of this episode, dentists will be able to:Apply a “just-in-time” approach to continuing development, prioritising the competencies relevant to the cases in front of them over isolated advanced techniques.Differentiate time-saving efficiencies from quality-compromising shortcuts, and describe strategies to maintain clinical standards early in practice.Apply structured communication techniques to explain procedural risk, establish a patient’s treatment goal, and make a clear, defensible recommendation as part of va...
-
 Why is Dr Tif Qureshi doing Blood Tests for his Patients? Should YOU? – PDP275 15.07.2026 1h 2minYour patient brushes well, avoids sweets — and still keeps getting decay. What if the answer isn’t in their mouth at all?What if two inexpensive finger-prick tests told you more about a patient’s gum disease and implant prognosis than anything on the radiograph?And here’s the uncomfortable one: if the science is this clear, is not checking starting to look like a medico-legal risk? Especially for imlpant surgery!This is a conversation with Dr Tif Qureshi— the dentist who changed how the profession thinks about the lifelong patient, the envelope of function, and Align, Bleach, Bond. He’s gone down a new rabbit hole: metabolic health. In general practice he’s now doing blood tests — HbA1c and vitamin D — and making the case that the mouth isn’t connected to the body, it is the body. This isn’t about becoming a “biological dentist” (as you’ll hear, Tif is refreshingly blunt about the wilder end of that world). It’s about respecting the biology, screening sensibly, and helping patients where we’re genuinely placed to help. https://youtu.be/mt1MXLFCTp0 Watch PDP275 on YouTubeProtrusive Dental Pearl: Test Yourself FirstBefore you even think about introducing blood tests for your patients, ask whether you’re checking your own biomarkers at a sensible interval. The deepest way to understand this topic is to learn it on yourself and your family first — run your own HbA1c, vitamin D, iron, and liver and kidney markers, and see what the data tells you.Start quarterly, like hygienist visits, then stretch to six-monthly or annual once things look good. Getting invested in your own numbers is what makes better food and lifestyle choices actually stick — and it’s the honest starting point for ever offering this to a patient.What You’ll Take From This EpisodeThe metabolic lens — why one disordered glucose-and-insulin system sits under so much chronic and dental disease, and why dentistry is well placed to act on it.Sugar, redefined — why patients who avoid sweets still get decay, and how frequency of starchy carbs drives the problem.The two biomarkers that matter most — what HbA1c and vitamin D each tell you about caries, perio and healing.How to run it in practice — finger-prick logistics, what to test, and how to raise it on the medical history form.The medico-legal case — why documenting these markers can protect you before implant, graft and perio work.Highlights of This Episode00:00 Why Dentists Should Care About Blood Tests06:00 Metabolic Disease: The Root Cause Dentists Miss13:00 Why Starchy Carbs Cause Decay, Not Just Sugar15:50 HbA1c and Caries: What the SHIP Study Shows21:00 Insulin Resistance: The Hidden Driver of Gum Disease26:00 How to Talk to Patients About Diet Without Scaring Them31:00 Why Vitamin D Deserves a Place in Dentistry34:00 Vitamin D, Implant Failure and Perio Risk37:00 Blood Tests as Medico-Legal Defence42:00 What Dentists Should Test: HbA1c and Vitamin D44:00 How In-Practice Blood Testing Actually Works50:00 The Mouth Is the Body: Screening, Not Diagnosing51:00 Is This Biological Dentistry? An Honest Answer57:00 How to Learn Blood Testing for Your PracticeFrom the GuestDr Tif Qureshi qualified from King’s College London in 1992 and is a Past President of the British Academy of Cosmetic Dentistry. He is Founder and Clinical Director of IAS Academy, best known for pioneering Align, Bleach, Bond and Progressive Smile Design, and as a teacher of the Dahl concept. His current focus is metabolic health in general practice.👉 IAS Academy — Align, Bleach, Bond, the Dahl concept, and blood-testing / metabolic health trainingComing soon: Join Dr. Tif in one-day metabolic health programme. He has spent years connecting the dots between what’s happening in the mouth and what’s happening in the body. The results are undeniable: better outcomes, stronger case acceptance, and a rock-solid medico-legal position.This one-day course will change the way you practise. For good.👉Metabolic Health in DentistryReferences & Further ReadingStudies and sources referenced in this episode:Song I-S, et al. Severe Periodontitis Is Associated with Insulin Resistance in Non-abdominal Obese Adults. J Clin Endocrinol Metab, 2016;101(11):4251–4259. Insulin resistance as an independent risk factor for severe perio in normal-weight adults.Botelho J, et al. Vitamin D Deficiency and Oral Health: A Comprehensive Review. Nutrients, 2020;12(5):1471. Vitamin D across caries, periodontitis, orthodontic and surgical outcomes.Schmolinsky J, Kocher T, Rathmann W, Völzke H, Pink C, Holtfreter B. Diabetes status affects long-term changes in coronal caries – The SHIP Study. Sci Rep. 2019 Oct 30;9(1):15685. doi: 10.1038/s41598-019-51086-z. PMID: 31666549; PMCID: PMC6821733.Want more?If you enjoyed this episode, check out: Why do some Dentists find Dahl Distasteful? – PDP016. #PDPMainEpisodes #BeyondDentistry #CommunicationListen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 1.0 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes C and A.AGD Subject Code: 730 Oral Medicine, Oral Diagnosis, Oral PathologyAim & Learning OutcomesAim: To help dental practitioners understand the link between metabolic health and oral disease, and to evaluate whether simple in-practice biomarker screening has a place in their care of patients.Learning Outcomes — by the end of this episode, dentists will be able to:Describe how disordered glucose and insulin metabolism relates to caries, periodontal disease and healing outcomes, and explain what HbA1c and vitamin D each indicate.Apply a structured, non-alarmist approach to discussing diet and biomarker screening with patients, within the professional boundary of screening rather than diagnosing or prescribing.Evaluate the clinical and medico-legal case for documenting relevant biomarkers before periodontal and surgical treatment, and identify when to refer to a medical colleague.
-
 Mastering Pediatric Dentistry: Pulpotomy and Crown Techniques – PDP274 08.07.2026 56minFilling, stainless steel crown, pulpotomy or extraction — how do you actually decide on a deciduous tooth?Why is the lower first primary molar the one that always seems to flare up?When should you reach for silver diamine fluoride instead of the drill — and when is a child’s cooperation telling you to change the plan entirely?And how do you actually do a pulpotomy, step by step, without it blowing up under the crown?This is a paediatric dentistry masterclass with Dr Nidhi Kotak— “The Baby Tooth Dentist,”. It’s built for the general dentist who treats children and wants clearer rules: when to fill versus crown, how to read the radiograph, silver diamine fluoride, local anaesthetic and behaviour guidance, isolation, and a full pulpotomy and stainless steel crown technique. The through-line is simple — in children you decide fast, protect the airway, and treat for predictability rather than heroics. https://youtu.be/3OscfwF7SIQ Watch PDP274 on YouTubeProtrusive Dental Pearl: Strategic FlexibilityYou cannot be rigid when treating children. The mindset shift is to stop asking “what should be done for this child?” and start asking “what can be done for this child?” With children you have to be fast and efficient, and curveballs are constant — sometimes the parent is harder to manage than the child. So the plan has to bend.The worked example: you planned a conventional prepped stainless steel crown, but cooperation drops mid-appointment. Rather than abandon the visit, switch to a no-prep whole-crown approach and protect the tooth anyway. It stays in the child’s best interest — and it’s far kinder to your own mental health. It’s a mindset worth carrying into all of dentistry, not just children’s.What You’ll Take From This EpisodeWhen to fill vs crown — the surface rule for baby molars, why crowns are so predictable in children, and where composites still work.The “D” devil tooth — why the lower first primary molar flares up, and why mesial caries on a D is an automatic crown.Pulpotomy indications — the signs that say vital pulpotomy, the ones that say extraction, and why a pulp exposure in a primary tooth is an automatic pulpotomy.SDF, sedation and isolation — arresting decay without drilling, matching sedation to the child, and protecting the airway.The pulpotomy technique — a full step-by-step from caries removal to cementing the stainless steel crown, including the modern medicament choice.Highlights of This Episode00:00 TEASER00:59 Pediatric Dentistry for GDPs: The Strategic Flexibility Mindset07:24 Why GDPs Struggle Treating Children08:19 When to Fill vs When to Crown a Baby Tooth12:18 Class II vs Stainless Steel Crown: The Surface Rule13:41 Reading Pediatric Radiographs & When to Take Bitewings19:15 SDF vs Fluoride Varnish: When to Use Each22:37 Resin Infiltration (Icon) for Children’s Teeth25:15 Pulpotomy in Primary Teeth: When It’s Indicated26:19 The “D” Devil Tooth: Why Mesial Caries Means a Crown27:31 Hall Crowns and the Modified Whole Crown Technique27:48 Midroll38:39 Local Anaesthetic & Behaviour Guidance in Children40:38 Sedation Options: Oral, Nitrous & Intranasal46:22 Rubber Dam vs Isolite: Isolation for Kids48:59 How to Do a Pulpotomy: Step-by-Step Technique58:03 OUTRODr Nidhi Kotak is a dual US and Canadian board-certified paediatric dentist — a Diplomate of the American Board of Pediatric Dentistry and a Fellow of the Royal College of Dentists of Canada. Follow Dr. Nidhi for more paediatric dentistry tips 👉 @babytoothdentist on InstagramWant more?If you enjoyed this episode, check out: Zirconia vs Metal Hall Crowns vs Conventional with Dr Tim Keys – PDP227#PDPMainEpisodes #EndoRestorativeListen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 1.0 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes C AGD Subject Code: 430 Pediatric Dentistry.Aim & Learning OutcomesAim: To give dental practitioners a clear, decision-led approach to restorative paediatric dentistry — how to choose between filling, crowning, pulpotomy and extraction, how to manage caries conservatively, and how to carry out a pulpotomy and stainless steel crown safely.Learning Outcomes — by the end of this episode, dentists will be able to:Differentiate the presentations that indicate a direct restoration, a stainless steel crown, a vital pulpotomy, or an extraction in the primary dentition, using clinical and radiographic findings.Describe minimally invasive and behaviour-management options in children — silver diamine fluoride, fluoride varnish, resin infiltration, local anaesthesia, sedation and isolation — and select them appropriately for the individual child.Apply a step-by-step technique for a vital pulpotomy and stainless steel crown in a primary molar, including the current choice of medicament and cementation.
-
 Consent in Orthodontics Should Be Individualised – PDP273 03.07.2026 46minHow good is your consent for orthodontics — really?More adults are having ortho, and more GDPs are providing it. So which risks should you be discussing with every single patient — and which ones depend on the person in the chair?When a case is heading for a big overjet or a tricky rotation, is that a conversation you have at the start, or one you scramble to explain halfway through?And what actually makes a consent form legally valid — the signature, or everything around it?This episode brings together two perspectives you don’t often hear in the same room. Dr Zaid Esmailis a specialist orthodontist and founder of the Online Orthodontic Academy, who mentors GDPs through fixed and aligner cases. Dr Neel Jaiswal returns for the dento-legal view — he’s a dentist and the founder of Professional Dental Indemnity (PDI). Together with Jaz, they get very specific about what individualised consent looks like in practice, and how to build a process your patients remember and a court respects. https://youtu.be/YvsiIiX1Q1w Watch PDP273 on YouTubeProtrusive Dental Pearl: Make Your Patient Feel UniqueIt might be your 100th, 500th or 1,000th case — but for the patient in the chair, this is a significant event. Never forget that. A routine extraction is routine for you; for them it’s a big deal, and remembering that makes you a better communicator.To make a specific risk stick, make the patient feel unique. Point to their OPG: “Your sinus here is actually really interesting,” or “Did you know your roots are unusually long?” Patients remember a risk framed as if they’re a special case far better than a generic warning. Make it personal, and the consent becomes memorable.What You’ll Take From This EpisodeThe whole episode turns on one idea: generic, templated consent is no longer defensible — the skill is individualising the form to the patient in front of you. Premium members get the full breakdown; here’s the shape:The layers of valid consent — consent is like an onion; a signed form and a documented conversation each cover a gap the other leaves open.Individualising risk from the records — how the OPG and photos turn a generic warning (resorption, devitalisation, recession, relapse) into a patient-specific one.The two-appointment consent flow — records, individualised risks, thinking time, and why you sign or initial every line.The Class II Div 2 overjet trap — the case that looks like simple crowding and ends in a big overjet, and how to consent for it before you start.When to treat, add an option, or refer — the GDC line on offering all options, and building alternatives into the form.Highlights of This Episode:00:00 Teaser01:01 Consent in Orthodontics: Why It Has to Be Individualised02:59 Protrusive Dental Pearl: Make Your Patient Feel Unique07:58 What Makes Orthodontic Consent Different10:08 How Much Ortho Litigation Comes From Consent?11:53 What Makes Consent Valid and Patient-Specific12:26 Individualising Ortho Risk from the OPG13:11 Using the ClinCheck as a Consent Tool14:40 How to Structure the Consent Appointment15:30 Root Resorption, Devitalisation, Recession and Relapse19:37 Should You Initial Every Line of a Consent Form?21:50 Midroll27:11 Building a Multi-Layered Consent Process29:31 Consenting for Fees, Relapse and Retainers34:41 The Class II Div 2 Overjet Trap37:51 When Should a GDP Refer an Ortho Case?40:31 How to Learn Orthodontics with Mentorship47:01 OutroDr Zaid Esmail is a specialist orthodontist. He founded the Online Orthodontic Academy to teach GDPs orthodontics — assessment, diagnosis and treatment planning across fixed appliances and aligners — with one-to-one case mentorship. He’s extended a 10% discount to the community with the code PROTRUSIVE.👉 Online Orthodontic Academy — online ortho mentorship, fixed & aligners, Level 7 DiplomaDr Neel Jaiswal returned for the dento-legal perspective. He’s a dentist and the founder of Professional Dental Indemnity (PDI), which introduces dentists to insurance-based indemnity cover.Request a Quote for Insurance and Get £100 off👉 Professional Dental Indemnity (PDI) — insurance-based dental indemnityWant more?If you enjoyed this episode, check out: Consent Is Like An Onion – Are You Consenting Your Patients Correctly? – PDP113Tags#PDPMainEpisodes #OrthoRestorative #Communication Listen, Subscribe, Earn CPDListen: Subscribe to the Protrusive Dental Podcast on Spotify, Apple Podcasts, or YouTube.This episode is eligible for 0.5 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes AAGD Subject Code: 565 Documentation & Risk Management Aim & Learning OutcomesAim: To help dental practitioners obtain valid, individualised consent for orthodontic treatment — identifying the risks that apply to every patient, tailoring them to the individual, and structuring a consent process that is both comprehensible to the patient and defensible in law.Learning Outcomes — by the end of this episode, dentists will be able to:Describe the elements that make orthodontic consent valid and patient-specific, including the material-risk standard and the role of reasonable alternative treatments.Apply a structured, multi-layered consent process — individualising risk from the clinical records and documenting the discussion — to an individual orthodontic patient.Identify the case types and clinical situations that warrant additional consent, an alternative option, or onward referral to a specialist.
-
 Thinking About Teaching Dentistry? Here’s What You Need to Know First – IC076 01.07.2026 43minEver fancied teaching dental students part time… but no real idea how you’d actually get in?Are you the kind of person teaching would energise — or quietly drain?Is a PGCert in dental education actually worth it, or just wishy-washy theory?And the honest question nobody asks out loud: does it pay anything?This is an Interference Cast — the non-clinical arm of the podcast — with Dr Rima Hussain, a general dentist who teaches restorative dentistry to undergraduates at King’s a couple of days a week. It’s a candid look at what a career in dental education actually involves: how to get in, who thrives and who burns out, what the work is really like, and the honest truth about the pay and the rewards. The bigger theme: dentistry is a career you can mould in endless directions — and for the right person, teaching is one of the most energising of them. https://youtu.be/DzmcM-SbD68 Watch IC076 on YouTubeWhat You’ll Take From This EpisodeThe full self-assessment and the step-by-step route into a teaching role are in the Premium Notes. Here’s the shape of what we cover:Are you built for the classroom? — the two-camp self-check (energised vs drained) that predicts whether teaching will recharge you or wear you down.How to actually land a role — the ‘BDJ Jobs’ plus pick-up-the-phone route, and why “who you know” so often cuts through the application process.Relatability as a strength — why being closer to a student’s level can beat decades of experience for an absolute beginner.Back to basics — the “monkey see, monkey do” risk from YouTube and AI, and what the tutor’s real job becomes.The honest pay-and-balance picture — why you don’t do it for the money, what you do get, and how teaching and practice keep each other fresh.Highlights of This Episode00:00 Teaser01:08 Should You Teach Dentistry? How to Know If It’s for You04:39 How a General Dentist Gets Into Dental Education06:15 Signs You’re Suited to Teaching Dentistry08:52 Is a PGCert in Dental Education Worth It?12:07 How to Land a Clinical Teaching Post at a Dental School14:38 Why a Relatable Tutor Beats Decades of Experience16:52 How Dental Students Have Changed Since COVID19:20 Is Social Media and AI Helping or Hurting Dental Students?21:55 Midroll26:43 Why “Back to Basics” Beats Chasing Advanced Techniques29:20 How to Get a Teaching (or Associate) Job: Pick Up the Phone31:50 Why Dental Tutors Quit After Six Months36:29 The Most Rewarding Part of Teaching Dentistry38:46 Teaching, Practice and Pay: How to Avoid Burnout44:39 OutroFrom the GuestDr Rima Hussain is a general dentist who also teaches restorative (conservative) dentistry to undergraduates at King’s College London — a route she fell into via tutoring as a teenager and has been in since 2019. Her advice for anyone curious: you’re probably already teaching in some form, so try it; the worst case is you find it isn’t for you.👉 Reach Rima on InstagramReferences & Further ReadingMentioned in this episode:Rath T. StrengthsFinder 2.0. Gallup Press, 2007. The strengths-assessment book referenced for the “Learner” theme and the idea of building your career around your natural strengths. “Learner” is one of its 34 themes; the assessment is now delivered as CliftonStrengths.BDJ Jobs.The British Dental Journal jobs board where clinical tutor and academic posts are advertised, usually with short application windows.Want more?If you enjoyed this episode, check out: 2 Years Out of Dental School – Insights for New Grads – IC066#InterferenceCast #CareerDevelopment #BeyondDentistryListen, Subscribe, Earn CPDThis episode is eligible for 0.5 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes B AGD Subject Code: 770 Self-Improvement Aim & Learning OutcomesAim: To help dentists evaluate a part-time career in dental education — what the role involves, how to obtain one, and how to sustain it alongside clinical practice.Learning Outcomes — by the end of this episode, dentists will be able to:Identify the personal attributes and expectations that distinguish dentists who thrive in clinical teaching from those who do not.Describe the practical routes into a dental-school teaching post, including where posts are advertised and how a direct, proactive approach can work.Recognise the workload, financial and work-life-balance realities of part-time teaching, and strategies to avoid burnout while balancing teaching and practice.
-
 Putting the ENT into dENTistry – PDP272 24.06.2026 59minSleep, Airway and Mouth Breathing: An ENT’s Guide for DentistsCould a “normal” sleep study still be missing your patient’s airway problem?Why do women and children with real symptoms keep scoring “mild”?Should a mouth-breathing child see a myofunctional therapist — or an ENT first?And which four questions screen a child for sleep problems in under a minute?The roof of the mouth is the floor of the nose — so ENT and dentistry should be in constant dialogue. In practice, they rarely are. In this one, Dr David McIntosh— an Australian ear, nose and throat surgeon with a deep niche in sleep-disordered breathing — makes the case for why that has to change, and gives dentists practical ways to screen and refer. He is direct, analogy-rich and doesn’t mince words; expect a few positions that cut against the grain of how sleep apnoea is usually handled. https://youtu.be/QVEc0ocxTCc Watch PDP272 on YouTubeProtrusive Dental Pearl: When the Numbers MisleadDentists love data — the AHI, the cut-offs (over 5 is mild, over 30 is severe). But take those numbers with a pinch of salt: the thresholds are arbitrary, and a single score tells you nothing about why a patient has the problem.They don’t account for individual variability — especially in women and children, where a mild score can sit right alongside significant symptoms. Read the number with the anatomy and the phenotype — the clinical signs and the airway assessment — never instead of them.What You’ll Take From This EpisodeThis conversation reframes sleep-disordered breathing from a number on a report into something you can localise and refer. A sleep study tells you IF, not WHY — sleep-disordered breathing is the whole spectrum; a normal study doesn’t mean normal breathing.Phenotyping the airway — map the individual anatomical causes instead of trusting a single score.Why women get missed — the gender bias built into standard adult screening tools, and what to ask instead.The four-question filter for children — snore, mouth breathe, stop breathing, wake up tired: any ‘yes’ means refer.Treat the cause before the function — why myofunctional therapy comes after the obstruction is cleared, not before, and how expansion and surgery are matched to the anatomy.Highlights of This Episode00:00 Teaser01:00 Why ENT and Dentistry Should Be Talking02:51 Protrusive Dental Pearl: When Sleep Data Misleads You03:46 Meet the ENT Who Works With Dentists06:00 Sleep Physician, ENT or Dentist: Who Should Lead?07:26 Why Children and Adults Are Completely Different08:58 Sleep-Disordered Breathing Is Not the Same as Sleep Apnoea09:39 Why a Normal Sleep Study Doesn’t Mean Normal Breathing10:01 Same AHI, Different Cause: A Tale of Two Patients12:54 Why One Night’s Sleep Study Isn’t Enough13:44 Where the AHI Cut-Off Numbers Really Came From15:27 CPAP Explained: A Bridge, Not a Cure18:27 When Snoring Hides Something Serious19:10 What Phenotyping the Airway Actually Means20:27 Splint, CPAP, or Both?21:33 Why a CBCT Can Miss a Deviated Septum25:32 Is STOP-Bang Enough to Screen for Sleep Apnoea?26:06 Why the Epworth Sleepiness Scale Is a Blunt Tool26:50 Why STOP-Bang Is Biased Against Women31:17 Sleep Apnoea in Women: Mild on Paper, Severe in Life32:05 Midroll36:56 The Triad: Airway, TMD and Orthodontics37:12 The Three Most Common Causes of Night-Time Grinding39:41 The Four Questions That Screen a Child for Sleep Problems41:03 Tired vs Not Tired: The Sign That Changes Everything43:36 Should You Refer to Myofunctional Therapy Before an ENT?45:58 The Hidden Dangers of Forcing Nasal Breathing52:28 Maxillary Expansion vs Surgery: Which One Fixes It?54:51 How Dentists Can Assess Adenoids56:25 Save the Child First: The Drowning Analogy57:56 Where Dentistry and ENT Go From Here1:00:05 Outro – New-Look Premium Notes & CPD OutroFrom the GuestDr David McIntosh is an ear, nose and throat surgeon (MBBS, FRACS, PhD) with a special interest in sleep-disordered breathing and airway obstruction. A self-described compulsive educator, he is the author of several books on Amazon — including dENTal health, on the connection between ENT and dental disease, and Snored to Death, on the lesser-recognised causes of obstructive sleep apnoea in adults.References & Further ReadingSources discussed in this episode:Chervin RD, Hedger K, Dillon JE, Pituch KJ. Pediatric sleep questionnaire (PSQ): validity and reliability of scales for sleep-disordered breathing, snoring, sleepiness, and behavioral problems. Sleep Medicine, 2000;1(1):21–32. The 22-item PSQ; a score above 0.33 suggests sleep-disordered breathing.Loved This Episode? Try NextAirway Dentistry with Jeff Rouse – PDP229Listen, Subscribe, Earn CPDThis episode is eligible for 1 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes CAGD Subject Code: 730 – Oral Medicine, Oral Diagnosis, Oral Pathology (Sleep medicine)#PDPMainEpisodes #OralSurgeryandOralMedicineAim & Learning OutcomesAim: To help dental practitioners recognise sleep-disordered breathing across the whole airway, screen adults and children appropriately, and refer at the right time and to the right clinician.Learning Outcomes — by the end of this episode, dentists will be able to:Differentiate sleep-disordered breathing from obstructive sleep apnoea, and explain why a normal sleep study does not exclude clinically significant breathing problems.Apply a structured screening approach for adults and children, including recognising why standard adult tools under-detect sleep-disordered breathing in women and children.Evaluate when to refer for specialist airway assessment, and articulate why addressing anatomical obstruction should precede functional (myofunctional) therapy.
-
 Your Dental Assistant Can Make or Break You – IC075 17.06.2026 47minThe most important part of your surgery isn’t plugged in, mounted, or calibrated. It’s the person standing beside you.Have you ever dreaded walking into a beautiful practice with lovely patients — purely because of who you share the surgery with?What do you actually do, in the moment, when your assistant rolls their eyes at a request for rubber dam?And should you be friends with your assistant at all — or does that cross a line you’ll regret?This is an Interference Cast — a non-clinical but deeply practical episode — with Dr. Sarah Braun, a dentist in Australia and a fellow Protrusive Guidance member who DM’d to suggest this very topic. No course, no book, nothing to sell: just two clinicians comparing notes (and the odd scar) on the one relationship that quietly shapes your whole working life. It sits inside this month’s theme of the relationships that support your career. https://youtu.be/OyztRyPpcHM Watch IC075 on YouTubeWhat You’ll Take From This EpisodeThe full breakdown is in the Premium Notes; here’s the shape of the thinking that runs through the episode:Engagement is the whole game — the assistant relationship sets the mood of the room, the patient’s experience, and whether good people stay.Speak their language — appreciation only lands if it’s delivered in the form that particular person actually values.Appreciation is a verb — specific, named praise lands far harder than a vague “good job.”Let them, let me — you don’t control how someone reacts in the moment; you only control your response to it.Lead the room — dentistry is a performance, and the room takes its emotional cue from whoever is leading it.Highlights of this episode:00:00 TEASER01:13 Why This One Relationship Can Make or Break You03:49 A Non-Clinical Interference Cast: What to Expect04:47 Meet the Guest: Nine Years In, City to Country07:01 A Week in Private Practice09:15 How Much Does the Dentist–Assistant Relationship Matter?11:01 Engagement at Work: The Gallup Lens12:30 People Remember How You Made Them Feel14:21 When the Relationship Turns Toxic15:23 The Power Imbalance You Might Not See18:11 The First-Day Conversation20:52 Keeping Your Assistant Engaged22:23 Specific Praise Beats a Vague “Good Job”23:55 Midroll27:37 You Can Only Control Yourself29:34 The Eye-Roll Moment: Let Them, Let Me31:23 Off Days vs Patterns32:12 Appreciation, Gifting & Speaking Their Language35:32 Run the Relationship Like It Matters36:48 Friends With Your Assistant, or Keep Your Distance?39:08 A Best Friend at Work: The Engagement Link41:15 Advice for New Grads: Start With Time Management44:26 Teaching as a Tool: Show Your Working Out48:05 Wrap-Up & a Healthy Debate48:37 CPD Outro & the Protrusive VaultReferences & Further Reading:Sources and further reading from this episode:Chapman G. The Five Love Languages. Northfield Publishing, 1992. The five ways people give and receive appreciation — words of affirmation, quality time, acts of service, receiving gifts, and physical touch — applied here to the dentist–assistant relationship.Robbins M, Robbins S. The Let Them Theory. Hay House, 2024. The “let them / let me” reframe for releasing what you can’t control and owning your own response.Rath T. StrengthsFinder 2.0. Gallup Press, 2007. The CliftonStrengths assessment; “Learner” is one of its talent themes, referenced in the discussion of teaching as a way to engage your assistant.Gallup employee-engagement research. The Gallup Q12 engagement survey (including the validated “I have a best friend at work” item) and Gallup’s State of the Global Workplace reports. Source of the workforce-engagement framing in this episode. Exact figures vary by year — see Reviewer Note.Want more?If you enjoyed this episode, check out: How to Find a Mentor in 5 Seconds Flat! – IC058. #InterferenceCast #CareerDevelopment #Communication #BeyondDentistryListen, Subscribe, Earn CPD:This episode is eligible for 0.75 CE credit via the quiz on Protrusive Guidance.This episode meets GDC Outcomes A and BAGD Subject Code: 550 Practice Management and Human RelationsAim & Learning Outcomes:Aim: To help dental practitioners understand and strengthen the working relationship between dentist and dental assistant — recognising its impact on team engagement, patient experience and personal job satisfaction, and building practical habits to improve it.Learning Outcomes — by the end of this episode, dentists will be able to:Explain how the working relationship between a dentist and a dental assistant affects team engagement, the patient experience, and clinician wellbeing.Identify practical strategies for communicating appreciation and recognition in ways suited to the individual, and for involving an assistant according to their preferences.Apply self-management and emotional-regulation approaches to leading the surgery and responding constructively to interpersonal friction.
Podcast simili


Popolare in
Questo podcast compare anche nelle classifiche dei podcast di questi paesi.


